

The idea is straightforward and compelling: a single blood test that can detect signals of multiple cancers before symptoms appear. Multi-cancer early detection (MCED) tests have attracted enormous attention in recent years. Several are now commercially available. Yet their clinical utility, who benefits from them, and what to do with their results remain questions not fully settled in current evidence. For related reading, see our articles on liquid biopsy and cancer detection, ovarian cancer symptoms that are often missed, and oncolytic viral therapy for advanced melanoma. Key Takeaways What Are Multi-Cancer Early Detection Tests? Multi-cancer early detection tests are blood-based tests designed to detect cancer-derived biological signals circulating in the bloodstream, before symptoms develop, across a wide range of cancer types in a single assay. They are closely related to — but distinct from — liquid biopsy technology, which is also used for monitoring known cancers and detecting treatment resistance. MCED tests are specifically designed for population-level screening in people without a known cancer diagnosis. The most advanced commercially available MCED tests primarily look for circulating tumour DNA (ctDNA): small fragments of DNA shed by cancer cells into the blood, carrying specific patterns of methylation that distinguish cancer-derived DNA from normal cell-derived DNA. The Galleri test (developed by GRAIL), the most clinically studied MCED test to date, uses methylation-based analysis of cell-free DNA to simultaneously screen for over 50 cancer types. How Do Multi-Cancer Early Detection Tests Work? When cells die, they release fragments of their DNA into the bloodstream. Cancer cells do the same, but their DNA carries distinctive molecular signatures. MCED tests isolate cell-free DNA from a blood sample and use machine learning algorithms to detect whether cancer-derived DNA is present and, if so, to predict which tissue type the signal most likely originated from. For a deeper explanation of how AI is being applied to cancer detection and diagnosis, see our article: AI Is Now Helping Diagnose Cancer: What That Means for You as a Patient. What Does the Clinical Evidence Show? The most robust published data comes from studies of the Galleri test. In the PATHFINDER study, published in The Lancet in 2023, the test was offered to over 6,600 adults aged 50 and older. Key findings: Key limitations from current evidence: Which Cancers Can Multi-Cancer Early Detection Tests Find? For context on how targeted screening works for specific cancers, see our articles on low-dose CT scan for lung cancer screening and colorectal cancer in young adults. Who Should Consider a Multi-Cancer Early Detection Test? Current clinical guidance from major oncology organisations is still evolving. The American Society of Clinical Oncology (ASCO) has published interim guidance noting that MCED tests may offer value in certain higher-risk populations. In practical terms: For an age-structured guide to when standard cancer screening should begin, see: When Should You Start Cancer Screening? An Age-Wise Guide for Men and Women. What Happens After a Positive Multi-Cancer Early Detection Result? A positive MCED result initiates a diagnostic workup guided by the predicted tissue of origin. The process typically involves: If a cancer diagnosis is confirmed after workup, our article on what happens in the first 30 days after a cancer diagnosis provides a practical guide to next steps. Importantly, approximately 60% of positive MCED results in current studies do not result in a confirmed cancer diagnosis. A negative result should not be used to defer or skip existing recommended cancer screening. What Are the Limitations of Multi-Cancer Early Detection Tests? How Do Multi-Cancer Early Detection Tests Fit Into a Broader Cancer Screening Strategy? Discuss your personal and family history of cancer with your doctor. See also: The Importance of Regular Health Check-ups for Cancer Prevention. For a complete overview of available cancer screening tests and recommended ages, see: When Should You Start Cancer Screening? Is This the Right Decision for You? Multi-cancer early detection tests represent a genuinely new tool in cancer early detection, one that is promising but not yet proven to reduce mortality at the population level. Consult Dr. Namratha Sai Reddy’s clinic if you or a loved one wants to: When Should Someone With a Positive MCED Result Seek Urgent Attention? If new symptoms emerge that suggest possible cancer progression or an acute complication, do not wait for a scheduled appointment. Go to the nearest emergency department or contact your oncologist the same day. Medical References Frequently Asked Questions 1. What is a multi-cancer early detection test? It is a blood test that analyses biological signals, primarily patterns in circulating tumour DNA, to detect cancer across 50 or more cancer types from a single blood draw, before symptoms appear. 2. How accurate are multi-cancer early detection tests? Current MCED tests have high specificity (approximately 99.5%) but moderate sensitivity (they detect roughly 16 to 40% of Stage I cancers and a higher proportion of later-stage cancers). Overall cancer detection rates vary by cancer type and stage. 3. Does a positive MCED test mean I have cancer? Not definitively. A positive result means a cancer signal has been detected in your blood. Approximately 40 to 60% of positive results in clinical studies are ultimately confirmed as cancer after diagnostic workup. 4. Does a negative MCED result mean I am cancer-free? No. A negative result means no cancer signal was detected above the test’s threshold. MCED tests miss a substantial proportion of early-stage cancers. A negative result should not replace standard age-appropriate cancer screening. 5. Do multi-cancer early detection tests replace colonoscopy, mammography, or other standard tests? No. MCED tests are designed to complement, not replace, established cancer screening tests. 6. Who should get a multi-cancer early detection test? Adults aged 50 and older with average to elevated cancer risk, particularly those with a family history of multiple cancers or cancers without standard screening, are most commonly discussed as appropriate candidates. 7. How often should an MCED test be repeated? Current guidance suggests annual testing for those who choose to use MCED tests as part of their screening programme, though optimal

Lymphoma Symptoms: Painless Neck Lump, Night Sweats and Unexplained Weight Loss
A lump in the neck that does not hurt. Night sweats that soak through clothing and bedding. Weight loss that happens without any change in diet or exercise. Together, and particularly when they persist, they form one of the most recognisable symptom clusters in oncology: the classic presentation of lymphoma. Yet despite this, lymphoma is frequently diagnosed late. This article explains what lymphoma symptoms look like, why certain ones get missed, what the different types of lymphoma mean for your prognosis, and when a swollen lymph node needs to be taken seriously. For related reading, see our articles on multi-cancer early detection blood tests and understanding survivorship care after cancer treatment. Key Takeaways What Is Lymphoma and How Does It Develop? Lymphoma is a cancer that originates in lymphocytes, a type of white blood cell that plays a central role in the immune system. When lymphocytes undergo malignant transformation, they can accumulate in lymph nodes and other lymphatic tissues, causing the swelling and systemic effects that characterise lymphoma. Hodgkin lymphoma (HL): Characterised by the presence of Reed-Sternberg cells. It tends to spread in a predictable, contiguous pattern and is highly responsive to treatment, with cure rates exceeding 85 to 90% in early-stage disease. Non-Hodgkin lymphoma (NHL): A much larger and more heterogeneous group, encompassing over 60 distinct subtypes with widely varying behaviour. NHL accounts for roughly 90% of all lymphoma diagnoses. According to the World Health Organization, lymphoma collectively accounts for approximately 4 to 5% of all new cancer diagnoses globally. For context on why cancer cases are rising in younger adults, including blood cancers, see our article: Why Cancer Cases Are Increasing in Younger Adults. What Are the Symptoms of Lymphoma? Lymph Node Symptoms B Symptoms (Systemic Symptoms) The following three symptoms are formally designated as B symptoms in lymphoma staging and carry prognostic weight: Other Commonly Reported Symptoms Why Is a Painless Neck Lump So Often Dismissed? Most people associate pain with disease severity. A lymph node that swells in response to infection is typically tender, appears suddenly, and resolves within two to four weeks. A lymphomatous node, by contrast, tends to be painless, firm, rubbery in texture, and gradually enlarging over weeks to months. The clinical rule of thumb: an enlarged lymph node that has been present for more than four weeks, is growing rather than shrinking, is hard or rubbery rather than soft, or is accompanied by any B symptom warrants investigation beyond simple observation. Who Is at Highest Risk for Lymphoma? What Are the Early Signs of Lymphoma to Watch For? How Is Lymphoma Diagnosed and Staged? Diagnosis always requires tissue, which means a lymph node biopsy is essential. No combination of imaging and blood tests alone is sufficient to confirm lymphoma. For a broader look at how blood-based cancer detection is evolving, see our article on liquid biopsy in cancer detection. For context on how AI tools are supporting cancer diagnosis, see AI in cancer detection and treatment. How Is Lymphoma Treated? Hodgkin Lymphoma Non-Hodgkin Lymphoma For more on managing the side effects of chemotherapy used in lymphoma treatment, see: Common Chemotherapy Side Effects and How to Manage Them. Is This the Right Concern for You? A painless lump that persists, unexplained weight loss, or drenching night sweats are symptoms that warrant evaluation. Consult Dr. Namratha Sai Reddy’s clinic if you or a loved one is experiencing: When Should Lymphoma Patients Seek Urgent Medical Care? If any of these occur, go to the nearest emergency department or call emergency services immediately. Medical References Frequently Asked Questions 1. What are the first signs of lymphoma? The most common early signs are a painless swollen lymph node (most often in the neck, armpit, or groin), unexplained fatigue, drenching night sweats, and unintentional weight loss. 2. Why are lymphoma lumps painless? Unlike nodes enlarged by infection, lymphomatous nodes tend not to cause pain because they grow slowly and do not trigger the same acute inflammatory response. 3. What are B symptoms in lymphoma? B symptoms are drenching night sweats, unexplained fever above 38 degrees Celsius, and unexplained weight loss of more than 10% of body weight over six months. Their presence at diagnosis carries prognostic significance. 4. Is a painless neck lump always lymphoma? No. Most painless neck lumps are benign. However, a neck lump that has been present for more than four weeks, is growing, is firm or rubbery, or is accompanied by B symptoms warrants medical evaluation. 5. What is the difference between Hodgkin and non-Hodgkin lymphoma? Hodgkin lymphoma is defined by the presence of Reed-Sternberg cells and tends to affect younger adults with a very high cure rate. Non-Hodgkin lymphoma is a broad category of over 60 subtypes, far more common overall. 6. Can lymphoma be cured? Many forms of lymphoma are curable. Hodgkin lymphoma has a cure rate exceeding 85% in early stages. Many aggressive NHL subtypes are also curable with standard chemotherapy regimens. 7. How is lymphoma diagnosed? Lymphoma is diagnosed by biopsy of an enlarged lymph node, followed by imaging (usually PET-CT) for staging. Blood tests, bone marrow biopsy, and molecular profiling are also part of the standard workup. 8. How long can someone have lymphoma without knowing? Indolent (slow-growing) lymphomas can be present for years before causing enough symptoms to prompt evaluation. Aggressive lymphomas typically cause symptoms within weeks to months of onset. 9. Is night sweating always a sign of lymphoma? No. Night sweats are common and have many causes including menopause, infection, anxiety, and medications. Lymphoma-related night sweats are typically drenching and occur repeatedly alongside other symptoms. 10. What should I do if I have a painless lump in my neck? If the lump has been present for more than four weeks, is growing, is not clearly associated with a recent infection, or is accompanied by weight loss, night sweats, or fever, see your doctor. This article is for informational purposes and does not replace professional medical advice. Always consult your oncologist before making decisions about your

Ovarian Cancer Symptoms: Why Bloating and Back Pain Are Often Missed
Ovarian cancer is frequently called a silent killer, but that description is not entirely accurate. Most women with ovarian cancer do experience symptoms. The real problem is that those symptoms are easy to dismiss and often not recognised as warning signs of cancer until the disease has already reached an advanced stage. This article explains what ovarian cancer symptoms actually look like, why they are missed so often, who is most at risk, and when a symptom that seems ordinary deserves urgent investigation. For related reading, see our articles on multi-cancer early detection blood tests and what survivorship care looks like once cancer is in remission. Key Takeaways What Is Ovarian Cancer and Why Is It So Frequently Diagnosed Late? Ovarian cancer is a malignancy that originates in the ovaries, the fallopian tubes, or the peritoneum. The most common type is epithelial ovarian cancer, which accounts for roughly 90% of cases. The ovaries sit deep in the pelvis, and a tumour can grow to a considerable size before causing noticeable symptoms. There is also no reliable, widely available screening test for the general population, unlike cervical cancer, which has the Pap smear. According to the American Cancer Society, the five-year survival rate for ovarian cancer diagnosed at a localised stage is over 90%. When diagnosed at a distant stage, it falls to approximately 31%. This survival gap makes earlier recognition of symptoms clinically critical. For context on when to begin cancer screening, see our age-wise guide: When Should You Start Cancer Screening? What Are the Symptoms of Ovarian Cancer? The four symptoms most consistently identified in ovarian cancer patients across large studies are: Additional symptoms that are commonly reported but receive less attention include: Why Are Bloating and Back Pain So Often Missed as Ovarian Cancer Symptoms? Bloating is one of the most common complaints in any general practice setting. It is a cardinal feature of irritable bowel syndrome, a common side effect of dietary choices, and a frequent premenstrual symptom. Back pain is even more commonly attributed to musculoskeletal causes or disc problems. Research published in the British Journal of General Practice found that women with ovarian cancer visit their GP an average of three times before the correct diagnosis is made. The clinical lesson is that bloating or back pain that is new, persistent, occurs frequently (more than 12 days per month), and does not resolve with standard treatment deserves pelvic assessment, not just symptomatic management. Who Is at Highest Risk for Ovarian Cancer? Obesity: Excess body weight significantly increases ovarian cancer risk. See our full article on how obesity increases cancer risk for the broader picture. What Are the Early Signs of Ovarian Cancer to Watch For? How Is Ovarian Cancer Diagnosed and Staged? Diagnosing ovarian cancer involves a combination of clinical examination, blood tests, and imaging. For a broader look at how blood-based testing is evolving in oncology, see our article on liquid biopsy and cancer detection. How Is Ovarian Cancer Treated? Treatment depends on the stage at diagnosis, the histological subtype, and the patient’s genetic profile. For an overview of how targeted therapies and immunotherapy work in cancer treatment, see our article on targeted therapy versus chemotherapy. Is This the Right Concern for You? If you or a loved one has been experiencing persistent bloating, pelvic pain, back pain, or urinary changes that are new and do not resolve, a pelvic assessment is warranted. Consult Dr. Namratha Sai Reddy’s clinic if you or a loved one is experiencing: When Should Women Seek Urgent Medical Care? If any of these occur, go to the nearest emergency department or call emergency services immediately. Medical References Frequently Asked Questions 1. What are the early symptoms of ovarian cancer? The earliest symptoms include persistent bloating, pelvic or abdominal pain, feeling full quickly, and urinary urgency or frequency. These symptoms are often subtle and easy to attribute to other causes. 2. Why is ovarian cancer called a silent killer? Because its early symptoms closely mimic common, benign conditions like irritable bowel syndrome or bladder infections, most cases are not diagnosed until the cancer has spread beyond the ovary. 3. Can back pain be a sign of ovarian cancer? Yes. Lower back pain, particularly when it is persistent, has no clear musculoskeletal explanation, and occurs alongside other pelvic or abdominal symptoms, can be a sign of ovarian cancer that is frequently overlooked. 4. What does ovarian cancer bloating feel like? Ovarian cancer bloating tends to be persistent and present on most days. It does not resolve after bowel movements and is not clearly tied to specific foods. It may be accompanied by visible abdominal distension or a feeling of pressure. 5. How is ovarian cancer diagnosed? Diagnosis involves a pelvic examination, transvaginal ultrasound, CA-125 blood test, and CT scan for staging. Definitive diagnosis requires surgical biopsy and pathological examination of removed tissue. 6. What is CA-125 and is it a reliable test for ovarian cancer? CA-125 is a blood tumour marker that is elevated in many ovarian cancers but can also be raised by benign conditions. It is not reliable enough to diagnose ovarian cancer on its own but is useful for monitoring treatment response. 7. Who should be tested for BRCA mutations? Women with a personal or family history of ovarian cancer, breast cancer (particularly at a young age or bilateral), fallopian tube cancer, or Ashkenazi Jewish ancestry should discuss BRCA genetic testing with their doctor. 8. Is ovarian cancer hereditary? Approximately 15 to 20% of ovarian cancer cases are linked to inherited gene mutations, most commonly BRCA1 and BRCA2. The majority of cases are sporadic. 9. What is the survival rate for ovarian cancer? Survival rates vary significantly by stage. When detected at a localised stage, the five-year survival rate exceeds 90%. For advanced-stage disease that has spread to distant organs, it is approximately 31%. 10. What should I do if I have persistent bloating and back pain? If bloating, pelvic pain, back pain, or urinary symptoms are
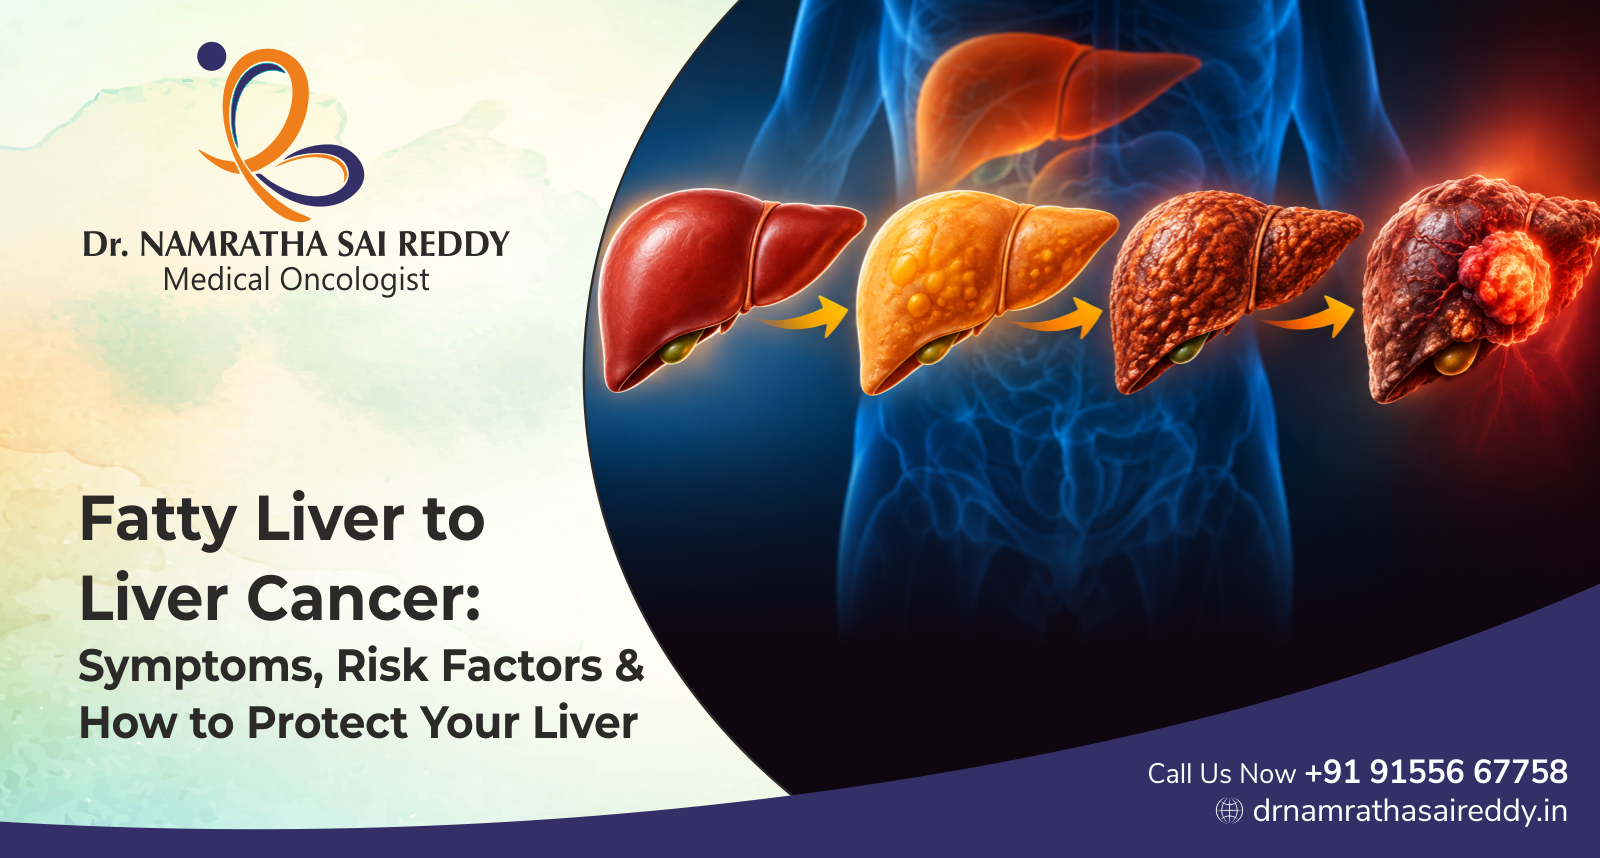
Fatty Liver to Liver Cancer: Symptoms, Risk Factors and How to Protect Your Liver
Fatty liver disease is among the most common conditions affecting adults today, yet most people dismiss it as a minor inconvenience rather than a potential gateway to something far more serious. What begins as excess fat accumulating in liver cells can, over years and decades, quietly progress through inflammation, scarring, and cirrhosis before arriving at hepatocellular carcinoma, the most common form of liver cancer. This article explains how and why that progression happens, what symptoms to watch for at each stage, and what you can do now to protect your liver before damage becomes irreversible. For related reading, see our article on obesity and cancer risk, and what survivorship care looks like once cancer is in remission. Key Takeaways What Is Fatty Liver Disease and Why Does It Matter? Fatty liver disease, now formally called metabolic dysfunction-associated steatotic liver disease (MASLD), occurs when more than 5% of the liver’s weight is made up of fat. In most cases, the liver continues to function adequately and the condition produces no symptoms. But the liver is not a passive bystander. When fat accumulates continuously, it can trigger a low-grade inflammatory response inside the liver tissue, a condition called metabolic dysfunction-associated steatohepatitis (MASH, formerly NASH). Over time, that inflammation causes liver cells to die and be replaced by fibrous scar tissue, a process called fibrosis. When fibrosis becomes extensive and widespread, the liver loses its normal architecture and function. This is cirrhosis. According to the World Health Organization, liver cancer is the sixth most commonly diagnosed cancer and the third leading cause of cancer-related deaths worldwide. In India, liver cancer incidence has been rising steadily, driven in part by the growing burden of metabolic disease, viral hepatitis, and alcohol-related liver damage. What Are the Symptoms of Fatty Liver Disease? Simple fatty liver (MASLD without inflammation) is almost always silent. Most people who have it do not know until a routine blood test reveals mildly elevated liver enzymes or an abdominal ultrasound done for another reason shows a bright, echogenic liver. As fatty liver progresses toward MASH and fibrosis, symptoms may begin to emerge, though they remain nonspecific: By the time cirrhosis develops, symptoms become more pronounced: What to avoid: Do not wait for symptoms to appear before getting your liver health checked. See our guide on the importance of regular health check-ups for cancer prevention. By the time liver cancer causes noticeable symptoms, it has often already advanced to a stage where curative treatment is more difficult. What Are the Early Signs of Liver Cancer? Who Is Most at Risk of Progressing from Fatty Liver to Liver Cancer? Not everyone with fatty liver will develop liver cancer. Obesity is one of the strongest modifiable risk factors and significantly accelerates the progression from fatty liver to MASH and cirrhosis. Other major risk factors include: How Is Fatty Liver Progression and Liver Cancer Diagnosed? Diagnosing fatty liver disease involves a layered approach. For context on how liquid biopsy and advanced blood tests are changing cancer detection, see our article on liquid biopsy and cancer detection. How Can You Protect Your Liver and Reduce Liver Cancer Risk? Get vaccinated against hepatitis B: One of the most effective liver cancer prevention measures available. See our article on vaccines for cancer survivors and prevention for related vaccination guidance. How Is Liver Cancer Treated? Treatment depends entirely on the stage of HCC and the patient’s overall health. For an overview of how targeted therapies differ from chemotherapy in cancer treatment, see our article on targeted therapy versus chemotherapy. Is This the Right Concern for You? Liver cancer risk from fatty liver is real but not inevitable. Consult Dr. Namratha Sai Reddy’s clinic if you or a loved one is experiencing: When Should Liver Disease Patients Seek Urgent Medical Care? If any of these occur, go to the nearest emergency department or call emergency services immediately. Medical References Frequently Asked Questions 1. Can fatty liver disease really lead to liver cancer? Yes. While most fatty liver cases remain stable, a subset progresses through inflammation and scarring (cirrhosis) to hepatocellular carcinoma, the most common form of liver cancer. The risk is highest in patients who develop cirrhosis. 2. How long does it take for fatty liver to progress to liver cancer? Progression from fatty liver to MASH to cirrhosis typically takes one to two decades, though metabolic risk factors like diabetes and obesity can accelerate it. Not all cases progress. 3. What are the first signs of liver cancer? Early liver cancer often has no symptoms. When symptoms appear, they include unexplained weight loss, upper right abdominal pain or fullness, loss of appetite, and worsening jaundice in someone with known liver disease. 4. Is fatty liver reversible? Yes. Early-stage fatty liver (without significant fibrosis) is reversible with sustained lifestyle changes including weight loss, dietary improvement, and alcohol cessation. Advanced fibrosis and cirrhosis are not fully reversible, though progression can be slowed. 5. Who should be screened for liver cancer? Current guidelines recommend HCC surveillance with ultrasound and AFP testing every six months for all patients with cirrhosis, regardless of cause, and for certain high-risk patients with chronic hepatitis B even without cirrhosis. 6. Does alcohol cause fatty liver and liver cancer? Yes. Alcohol is both a direct cause of fatty liver and an independent liver cancer risk factor. It also significantly worsens metabolic fatty liver disease when both conditions are present. 7. What diet is best for fatty liver? A Mediterranean-style diet, rich in vegetables, legumes, whole grains, olive oil, and lean protein, with limited sugar and refined carbohydrates, has the strongest evidence for reducing liver fat and inflammation. 8. Can liver cancer be treated if caught early? Yes. Early-stage HCC detected within transplant criteria or suitable for surgical resection or ablation has significantly better outcomes than advanced disease. 9. Are there medications for fatty liver? Resmetirom (Rezdiffra) received FDA approval for MASH with moderate to advanced fibrosis, the first drug approved specifically for this indication. GLP-1 receptor agonists also
Understanding Oncolytic Viral Therapy: A New Option for Advanced Melanoma
If standard immunotherapy has stopped working for advanced melanoma, a new class of treatment called oncolytic viral therapy is now available. On August 6, 2026, the FDA granted accelerated approval to vusolimogene oderparepvec-wtpg (Tudriqev), a genetically modified oncolytic virus, in combination with nivolumab for adults with unresectable advanced cutaneous melanoma that has progressed on a prior PD-1 blocking immunotherapy regimen. This article explains what oncolytic viral therapy is, how it works against melanoma, and who may be eligible. For related reading, see our articles on personalised mRNA cancer vaccines and the immune-based treatments that followed COVID-19 research andwhat survivorship care looks like once cancer is in remission. Key Takeaways What Is Oncolytic Viral Therapy and How Does It Work Against Cancer? Oncolytic viral therapy is a form of cancer treatment that uses a modified virus, engineered so it can infect and multiply inside cancer cells while sparing healthy tissue. Cancer cells often have weakened antiviral defenses compared to normal cells, which allows the virus to selectively take hold inside the tumor. Once inside, the virus replicates until the cancer cell breaks open, or lyses, releasing new virus particles that go on to infect neighboring tumor cells. This process also exposes the immune system to tumor material and inflammatory signals it wouldn’t otherwise see, effectively turning the injected tumor into a trigger for a broader immune response against melanoma elsewhere in the body, even in lesions that weren’t directly injected. According to the American Association for Cancer Research, melanoma is the fifth most common cancer in the United States, and in 2026 alone, an estimated 112,000 people were expected to be diagnosed with it in the country. How Does Vusolimogene Oderparepvec (Tudriqev) Treat Advanced Melanoma? Tudriqev is built from a genetically modified herpes simplex virus, type 1 (HSV-1), engineered to remove the genes responsible for causing disease in humans while adding genes that boost its cancer-fighting ability. It carries a fusogenic protein derived from gibbon ape leukemia virus, which helps cancer cells fuse together and die more efficiently, along with a gene for GM-CSF, a protein that helps recruit and activate immune cells at the tumor site. Full prescribing and dosing details are available from the FDA’s official approval announcement and from Replimune’s own announcement of the approval. Can Oncolytic Viral Therapy Replace Immunotherapy for Melanoma? Not exactly. Oncolytic viral therapy for melanoma is currently approved to be used together with nivolumab, an existing immunotherapy drug, not as a replacement for it. The approval specifically covers patients whose melanoma has already progressed after a course of anti-PD-1 based immunotherapy, so it functions as a next step rather than a substitute for first line immunotherapy. What Does the Clinical Trial Evidence Show for This Melanoma Treatment? The approval is based on results from the IGNYTE trial, an open label, multiregional study that enrolled 140 adult patients with Stage IIIB, IIIC, or IV unresectable advanced melanoma who had progressed after at least eight consecutive weeks of prior anti-PD-1 based therapy. Does a 24% Response Rate Mean Most Patients Won’t Benefit? Not quite, and this is an important nuance. A 24.2% objective response rate means roughly one in four patients had a measurable shrinkage of their tumors, but this doesn’t capture the full picture of clinical benefit, since some patients may experience disease stabilization without a formal “response” by trial criteria. For a patient population that has already progressed on immunotherapy and previously had very limited options, a durable response lasting over a year in a meaningful subset of patients represents real progress. What Side Effects and Precautions Are Associated With Oncolytic Viral Therapy? Because Tudriqev is a modified live virus, it comes with specific safety considerations beyond those of typical cancer drugs. For patient-focused guidance on preparing for treatment and what to expect, the AIM at Melanoma Foundation offers additional resources for patients and caregivers navigating this new treatment option. What Are the Early Signs of Melanoma to Watch For? Recognizing melanoma early gives patients access to more treatment options, including surgery, before the disease becomes advanced or unresectable. How Is Advanced Melanoma Diagnosed and Monitored During Treatment? Diagnosing and staging advanced melanoma, and tracking how it responds to treatments like oncolytic viral therapy, typically involves several steps. What to avoid: Don’t delay evaluation of a changing mole or skin lesion, since earlier stage melanoma has far more treatment options than advanced disease. Don’t assume that progression on one immunotherapy regimen means no further treatment options exist. Newer approaches like oncolytic viral therapy are specifically designed for this situation. Is Oncolytic Viral Therapy the Right Option for You or a Loved One? Oncolytic viral therapy represents a genuinely new treatment category for advanced melanoma, but it isn’t the right fit for every patient. Eligibility depends on prior treatment history, the location and number of melanoma lesions, and overall health. This is a decision best made together with a medical oncologist experienced in melanoma care. Consult Dr. Namratha Sai Reddy’s clinic if you or a loved one is experiencing: Call +91 91556 67758 or book an appointment online to schedule a consultation. When Should Melanoma Patients Seek Urgent Medical Care? Certain symptoms during melanoma treatment need prompt medical attention rather than waiting for a routine follow up. If any of these occur, go to the nearest emergency department or call emergency services right away. Medically Reviewed & Approved By Dr. B. Namratha Sai Reddy Medical Oncologist, American Oncology Institute, Nallagandla, Hyderabad Dr. Namratha leads the Medical Oncology Department at American Oncology Institute, Nallagandla. Medical References Frequently Asked Questions 1. What is oncolytic viral therapy for melanoma? It’s a cancer treatment that uses a genetically modified virus, injected directly into tumors, to infect and destroy cancer cells while triggering an immune response against melanoma elsewhere in the body. 2. What is Tudriqev and how is it used for melanoma? Tudriqev (vusolimogene oderparepvec-wtpg) is a genetically modified herpes simplex virus based oncolytic therapy, approved in combination with nivolumab for adults with advanced melanoma that has
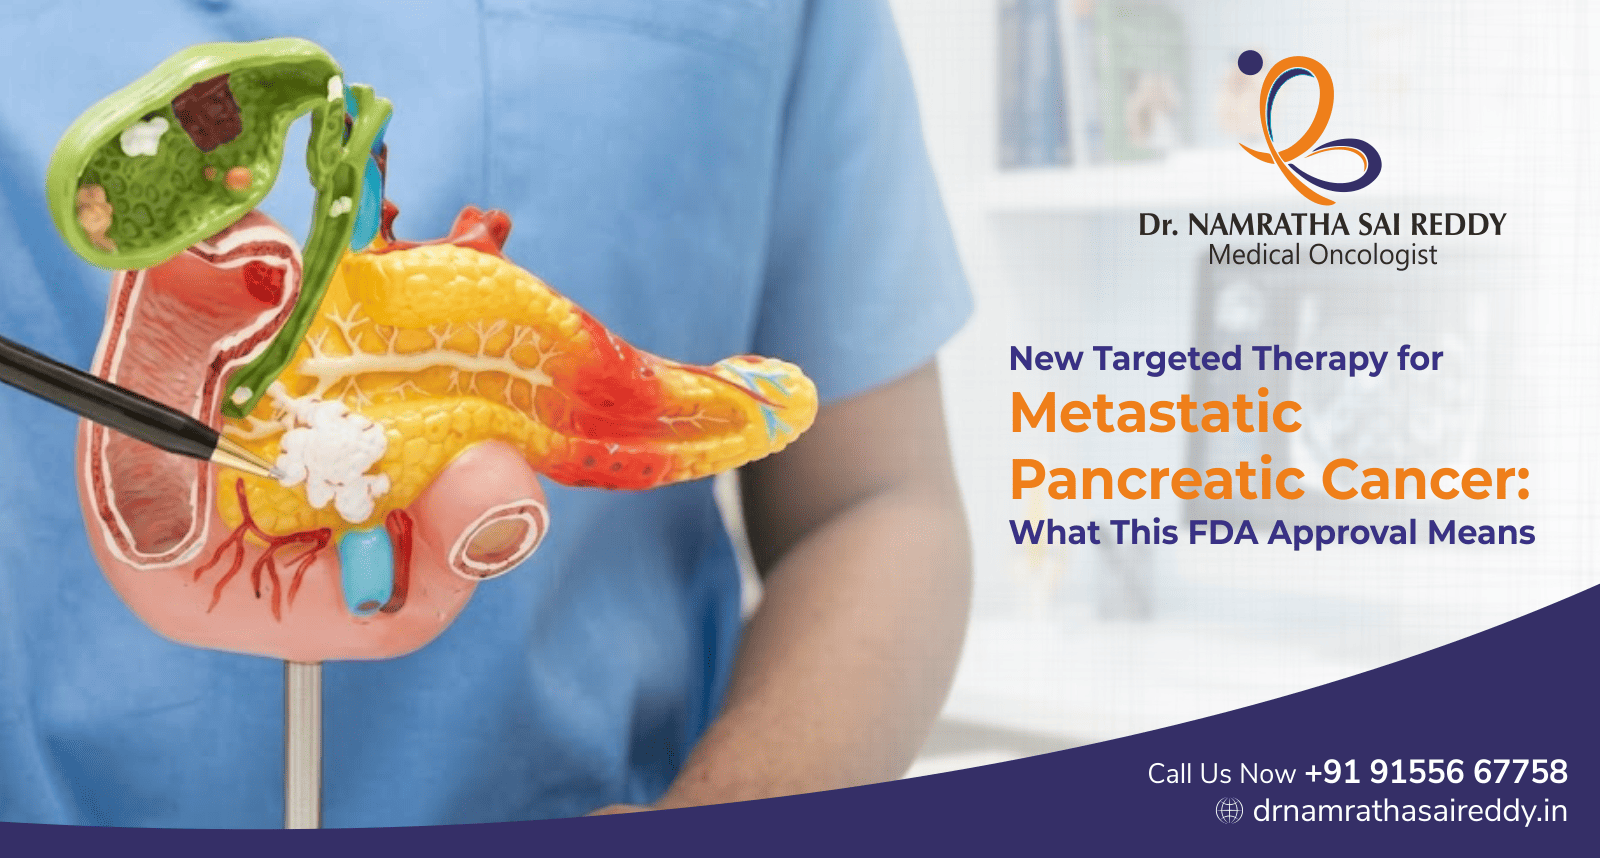
New Targeted Therapy for Metastatic Pancreatic Cancer: What This FDA Approval Means
Metastatic pancreatic cancer has long been one of the most difficult cancers to treat, with limited options once it stops responding to standard chemotherapy. That changed on August 26, 2026, when the FDA approved daraxonrasib (Rasonque), the first targeted therapy designed to block RAS, the protein responsible for driving growth in most pancreatic tumors. This guide explains what the approval means, who qualifies, and what patients and families should understand about this new option. For related reading, see our articles on why more non-smokers are being diagnosed with cancer driven by genetic mutations and what MRD testing means for cancer monitoring. Key Takeaways • Daraxonrasib (Rasonque) is the first targeted therapy approved specifically to block RAS, a protein that drives tumor growth in more than 90% of pancreatic adenocarcinoma cases. • In its pivotal trial, the drug nearly doubled median overall survival, extending it to 13.2 months compared with 6.7 months on standard chemotherapy, and reduced the risk of death by 60%. • It is approved for adults with metastatic pancreatic adenocarcinoma who have already had at least one prior systemic therapy, or who cannot tolerate multiagent chemotherapy. • It is taken as a once daily oral tablet, offering a less burdensome alternative to intravenous chemotherapy. • The FDA granted approval more than six months ahead of its scheduled review date, reflecting how strong the trial results were. • This is not a first line treatment. It becomes an option after chemotherapy has already been tried or is not suitable. What Is Pancreatic Adenocarcinoma and Why Is It So Hard to Treat? Pancreatic adenocarcinoma is the most common form of pancreatic cancer, arising from the cells lining the ducts of the pancreas. It is notoriously difficult to catch early because it often causes few or no symptoms in its initial stages. As a result, roughly 80% of patients are diagnosed only after the cancer has already spread beyond the pancreas, when treatment options become more limited. In the United States alone, there are an estimated 67,530 new cases of pancreatic cancer each year and about 52,740 deaths, making it one of the deadliest common cancers. This is the backdrop against which a genuinely new class of targeted therapy matters so much. What Is RAS and Why Does Targeting It Matter for Pancreatic Cancer? RAS is a protein that, in its normal form, helps regulate when and how cells grow. In pancreatic cancer, a mutation most often in the KRAS gene locks this protein into a constantly active, “always on” state, driving relentless tumor growth. More than 90% of pancreatic adenocarcinoma cases involve this kind of RAS pathway mutation, which is why researchers have spent decades trying to find a way to block it directly. • Ask your oncologist whether your tumor has been tested for RAS or KRAS mutations, since this determines whether targeted therapy is an option for you. • Understand that daraxonrasib works as a “molecular glue,” pairing with another protein in the cell to block active RAS signaling rather than trying to remove the mutated gene itself. • Know that this approach had been considered extraordinarily difficult to achieve for many years, which is part of why this approval is considered a landmark moment in pancreatic cancer care. Full details are available in the FDA’s official approval announcement. Does This New Drug Work for Everyone With Pancreatic Cancer? Not necessarily, and this is worth clarifying. The approval applies specifically to adults with metastatic pancreatic adenocarcinoma who have already received at least one prior systemic therapy, or who are not candidates for combination chemotherapy. It is not currently approved as a first line treatment, and its benefit is tied to the tumor being driven by the RAS pathway, which is common but not universal in pancreatic cancer. What Does the Clinical Trial Data Actually Show? The approval is based on the international phase 3 RASolute 302 trial, which enrolled 500 patients with previously treated metastatic pancreatic cancer across North America, Europe, and Asia. The results were substantial enough that they were presented at the 2026 American Society of Clinical Oncology Annual Meeting and published in the New England Journal of Medicine. • Median overall survival was 13.2 months with daraxonrasib compared with 6.7 months for investigator’s choice chemotherapy. • The risk of death was reduced by 60% compared with standard chemotherapy in the trial. • The drug received Breakthrough Therapy Designation and Orphan Drug Designation from the FDA, reflecting both its significance and the relatively small population it serves. Is Doubling Survival Time the Same as a Cure? No. A near doubling of median survival is a major step forward for a cancer with historically poor outcomes, but it does not mean the disease is cured. The goal of this therapy is to meaningfully extend life and improve disease control for patients who previously had very few effective options after chemotherapy stopped working. What Side Effects and Precautions Come With This Treatment? As with any systemic cancer therapy, daraxonrasib carries its own set of side effects that patients should discuss with their oncologist before starting treatment. • Regular blood work is needed to monitor for changes related to treatment, since RAS pathway inhibitors can affect normal cells that rely on the same signaling pathway. • Report any new or worsening skin changes, gastrointestinal symptoms, or unusual fatigue to your care team promptly. • Because it is an oral medication taken daily, consistency in dosing matters. Missed or irregular doses can affect how well the drug controls the cancer. • Discuss all other medications and supplements with your oncologist, since interactions are possible with
ROS1-Positive Lung Cancer: Symptoms and Signs of a Rare NSCLC Subtype
ROS1-positive non-small cell lung cancer (NSCLC) is a rare, genetically distinct form of lung cancer that behaves differently from typical smoking-related lung cancers. It tends to affect younger adults, often non-smokers, and its symptoms can be easy to miss or mistake for something less serious. If you’re trying to understand what ROS1-positive lung cancer looks like, from early warning signs to the newest treatment advances, this guide walks through what to watch for and when to see a doctor. For related context, see our articles on why more non-smokers are being diagnosed with lung cancer and what MRD testing means for cancer monitoring. Key Takeaways • ROS1-positive NSCLC occurs when the ROS1 gene fuses with another gene, driving uncontrolled cell growth. It accounts for up to 3% of all NSCLC cases. • It typically affects non-smokers in their 40s and 50s, which makes it easy to overlook since it doesn’t fit the classic lung cancer risk profile. • Early symptoms often overlap with common respiratory issues, including persistent cough, chest discomfort, and shortness of breath. • ROS1-positive NSCLC frequently spreads to the brain, so neurological symptoms like headaches or dizziness can also be an early sign. • A newly approved targeted therapy, zidesamtinib (Jideytro), offers a next option for patients whose cancer has progressed after a prior ROS1 inhibitor. • Diagnosis depends on molecular testing (biomarker testing) of the tumor, not just imaging, so ask specifically about ROS1 testing if lung cancer is suspected. What Is ROS1-Positive Non-Small Cell Lung Cancer? Non-small cell lung cancer (NSCLC) is the most common form of lung cancer overall, and within it, a small subset of tumors are driven by a specific genetic abnormality called a ROS1 gene fusion. This happens when the ROS1 gene fuses with part of another gene, causing the resulting protein to send constant “grow” signals to the cell, which leads to uncontrolled tumor growth. ROS1-positive NSCLC tends to be more aggressive than average and has a strong tendency to spread to the brain. Roughly 50,000 people worldwide are diagnosed with this subtype each year, and it’s notably common in people who have never smoked, which often delays diagnosis since lung cancer isn’t the first thing patients or even doctors initially suspect. 1. What Are the Early Symptoms of ROS1-Positive Lung Cancer? Because ROS1-positive NSCLC tends to occur in younger, non-smoking adults, early symptoms are frequently dismissed as a lingering cold, allergies, or stress-related fatigue. Recognizing the pattern early can make a meaningful difference in how quickly treatment starts. • A cough that persists for more than three weeks, especially if it’s new or has changed in character. • Chest pain or discomfort that worsens with deep breathing, coughing, or laughing. • Shortness of breath during activities that didn’t previously cause breathlessness. • Coughing up blood or blood-tinged mucus, even in small amounts. • Unexplained fatigue or a general sense of being unwell that doesn’t improve with rest. Can Lung Cancer Cause Symptoms Even in People Who Have Never Smoked? Yes, and this is one of the most important myths to correct about ROS1-positive lung cancer specifically. Because this subtype is driven by a gene fusion rather than tobacco exposure, it occurs disproportionately in lifelong non-smokers, often in their 40s and 50s. Patients and even clinicians can be slow to consider lung cancer in this group precisely because the traditional smoking-related risk factors are absent, which is why persistent respiratory symptoms in a non-smoker should not be automatically ruled out as low risk. 2. Can ROS1-Positive Lung Cancer Cause Symptoms in the Brain or Nervous System? Yes. ROS1-positive NSCLC has a strong tendency to spread to the brain, and in some cases, neurological symptoms appear before the lung symptoms are even noticed. • New or worsening headaches, particularly ones that are worse in the morning. • Dizziness, balance problems, or unexplained falls. • Vision changes, such as blurred or double vision. • New onset seizures in someone with no prior seizure history. • Subtle changes in memory, mood, or personality noticed by family members. Because brain involvement is common in this subtype, newer targeted drugs are specifically designed with the ability to cross the blood-brain barrier to control disease in the brain, which was a major limitation of some earlier treatments. 3. Why Does ROS1-Positive Lung Cancer Often Affect Non-Smokers and Younger Adults? This is one of the defining, and most confusing, features of ROS1-positive NSCLC. Unlike most lung cancers, which are strongly linked to cumulative tobacco exposure, ROS1 fusions arise from a specific genetic event within the tumor and are not caused by smoking history. This is part of a broader pattern researchers have observed of lung cancer rising among lifelong non-smokers, tied to gene fusions and mutations rather than external carcinogen exposure. • If you’re a non-smoker with persistent respiratory symptoms, mention this clearly to your doctor rather than assuming lung cancer is unlikely. • Ask about biomarker or molecular testing specifically, since routine imaging alone won’t identify a ROS1 fusion. • Family history of lung cancer in non-smokers is worth mentioning during evaluation, even though ROS1 fusions themselves are not typically inherited. 4. What Are the Warning Signs That ROS1-Positive Lung Cancer Is Progressing or Resistant to Treatment? Patients already being treated for ROS1-positive NSCLC with a targeted therapy (a ROS1 tyrosine kinase inhibitor) should watch for signs that the cancer is progressing or has developed resistance to that drug. • Return or worsening of symptoms that had previously improved on treatment, such as cough or
Multiple Myeloma Precautions: What New Treatment Combinations Mean for Patients
If you or a loved one has relapsed or refractory multiple myeloma, a newly approved treatment combination, iberdomide paired with daratumumab and dexamethasone, is opening up a fresh option after prior therapy stops working. This drug class, called a CELMoD (cereblon E3 ligase modulator), is the first of its kind approved for myeloma, and it comes with real benefits as well as specific precautions around blood clots, infections, and pregnancy risk that patients and caregivers need to know before starting treatment. For background on how myeloma is first identified, see our related read on early symptoms of blood cancers and our guide to chemotherapy side effects and recovery. Key Takeaways • A new oral drug class called CELMoDs (cereblon E3 ligase modulators) has received FDA accelerated approval for relapsed/refractory multiple myeloma, the first such approval of its kind. • The new combination (iberdomide plus daratumumab plus dexamethasone) nearly doubled the rate of deep, MRD-negative remission compared to a standard regimen in clinical trials. • It carries boxed warnings for blood clots and harm to a developing pregnancy, meaning strict monitoring and contraception precautions are required. • Low blood counts and infections are common side effects that need regular blood work and prompt reporting of fever or illness. • This treatment is for patients who have already tried at least one prior line of therapy; it is not a first-line option. • Talk to your oncologist about whether your prior treatment history and current health make you a candidate. What Is Multiple Myeloma and Why Does It Keep Coming Back? Multiple myeloma is a cancer that begins in plasma cells, a type of white blood cell made in the bone marrow that normally produces antibodies to fight infection. In myeloma, abnormal plasma cells multiply out of control, crowding out healthy blood cells and often causing bone damage, kidney problems, anemia, and a weakened immune system. It is typically a relapsing condition. Most patients respond to initial treatment, but the disease often returns, requiring new lines of therapy over time as earlier drugs stop working or the cancer develops resistance to them. This is exactly the situation the newest drug combinations are designed to address: what to do when myeloma comes back after earlier treatment. 1. What Is CELMoD Therapy and How Does Iberdomide Treat Multiple Myeloma? Iberdomide belongs to a brand new drug class called CELMoDs, which work by targeting and breaking down specific proteins inside myeloma cells. This slows cancer growth, triggers cancer cell death, and also boosts the immune system’s ability to attack the remaining cancer cells. It is taken as a daily pill in combination with daratumumab (an antibody infusion) and dexamethasone (a steroid). • Ask your oncologist whether you meet the criteria: at least one prior treatment line that included both a proteasome inhibitor and an immunomodulatory drug. • Understand that this is an oral medication taken alongside infusion based therapy, so your treatment schedule will involve both clinic visits and at home pills. • Clarify how long treatment is expected to continue. Generally, it continues until the disease progresses or side effects become unacceptable. For full prescribing and safety details, refer to the FDA’s official approval announcement. Can New Multiple Myeloma Drugs Like Iberdomide Cure the Disease? Not exactly, and this is an important myth to clear up. The goal of this combination is deep, sustained remission (measured as “MRD-negative complete response,” meaning no detectable cancer cells remain even with sensitive testing) rather than an outright cure. In trials, this deeper remission was achieved by roughly 4 in 10 patients on the new combination, compared to about 2 in 10 on the older comparator regimen. Deeper remission is linked to better long-term outcomes, but multiple myeloma is still generally considered a manageable, chronic cancer rather than a curable one. 2. Why Does the New Myeloma Treatment Combination Increase Blood Clot Risk? One of the most serious risks flagged for this drug combination is an increased chance of blood clots in the veins and arteries, serious enough that it carries an FDA boxed warning, the strongest safety warning a medication can carry. The exact mechanism is linked to how CELMoDs and immune-modulating drugs affect clotting factors and blood vessel walls. • Report any leg swelling, pain, warmth, sudden shortness of breath, or chest pain to your care team immediately. • Your doctor may prescribe blood thinning medication or aspirin alongside treatment as a preventive measure. • Stay as physically active as your condition allows, since prolonged immobility raises clotting risk. 3. Why Are Infections and Low Blood Counts Common During Iberdomide Treatment? Because CELMoD therapy affects the immune system and bone marrow, low white blood cell counts (neutropenia) and infections are common, occurring in a large majority of patients in clinical trials. This happens because the same pathways that help the drug attack cancer cells can also temporarily suppress the bone marrow’s production of healthy blood cells. • Expect frequent blood tests to monitor your white cell, red cell, and platelet counts throughout treatment. • Avoid close contact with people who are visibly sick, and stay current on recommended vaccinations as advised by your oncologist. • Report fever, chills, cough, or any new signs of infection right away. Don’t wait for your next scheduled visit. The National Cancer Institute provides general guidance on managing infection risk during cancer treatment. Does a Low Blood Count During Myeloma Treatment Always Mean the Treatment Is Failing? No, this is a common misconception. Low blood counts are usually a side effect of how the drugs work on the bone marrow, not a sign that the cancer is getting worse. Your

Cancer Is in Remission. What Happens Next? A Guide to Survivorship Care
Reaching remission is a major milestone, but it isn’t the end of your cancer care — it’s the start of a new phase called survivorship. This involves a structured follow-up plan covering surveillance for recurrence, management of late and long-term treatment effects, emotional and psychosocial support, and general health monitoring. The American Society of Clinical Oncology (ASCO) recommends every patient receive a formal Survivorship Care Plan at the end of active treatment, outlining exactly what comes next. An oncologist can help build a plan tailored to your specific diagnosis and treatment history. Just finished active treatment? Consult Dr. Namratha Sai Reddy to build a personalised survivorship care plan covering surveillance, side-effect management, and long-term wellbeing. Key Takeaways When should survivorship planning begin? Ideally, survivorship planning should begin as soon as active treatment ends, not months later. If you’ve completed treatment and haven’t received a written survivorship care plan, ask your oncology team for one at your next visit. What Does “Remission” Actually Mean? Remission means that signs and symptoms of cancer have decreased or disappeared on available testing. In many cases this is described as complete remission, meaning no detectable disease on standard scans and blood tests. It’s important to understand that remission is not always the same as “cured”, some cancers can recur, sometimes years later, which is precisely why structured follow-up remains essential even when you feel completely well. Is Survivorship Care Really a Separate Phase of Treatment? Yes. Survivorship medicine has been formally recognised as a distinct area of cancer care for nearly two decades. The concept was formalised by the Institute of Medicine’s landmark 2006 report, which highlighted the risks of patients being“lost in transition” between active treatment and long-term follow-up. That report outlined four key pillars of survivorship care: preventing recurrence and new cancers, surveillance for recurrence and late effects, intervening on the consequences of treatment, and coordinating care between oncology specialists and primary care providers. Today, survivorship care plans are considered standard of care across major cancer centres. How Many People Are Living as Cancer Survivors Today? The survivor population has grown dramatically as treatments have improved. As of 2026, it’s estimated there are over 20 million cancer survivors in the United States, up from around 15.5 million in 2016, and this number is projected to keep climbing. This growth reflects genuinely encouraging progress: the overall five-year relative survival rate for all cancers combined has reached a record 70%, and overall cancer mortality has declined by 34% since its peak in the early 1990s. As more people move successfully through treatment and into remission, survivorship care has become an increasingly central part of oncology. What’s Actually in a Survivorship Care Plan? A proper Survivorship Care Plan (SCP) has two core components, based on consensus recommendations developed by ASCO. Treatment Summary – a record of your diagnosis, stage, all treatments received, ongoing side effects, and, where relevant, any genetic testing or predisposing conditions. Follow-Up Care Plan covering: What Are “Late Effects” and Why Do They Matter? Late effects are health problems caused by cancer treatment that don’t appear until months, years, or even decades after treatment has ended, distinct from short-term side effects like nausea or fatigue, which typically resolve within weeks or months. Depending on the treatment received, late effects can include heart problems from certain chemotherapy drugs, organ damage from radiation exposure to a specific area, hormonal or fertility changes, secondary cancers, cognitive changes sometimes called “chemo brain,” and increased cardiovascular risk. This is exactly why a treatment summary matters so much: without a clear record of which drugs and which radiation fields were used, a primary care provider may not know which specific late effects to watch for down the line. Why Can’t My Regular Doctor Just Handle Follow-Up Without a Plan? They often can, but they need the right information to do it well, and this is one of the more overlooked gaps in cancer care. Survivorship care plans exist partly to solve this handoff problem, cancer treatment involves highly specific drug regimens, radiation doses, and organ-specific risks that a general practitioner isn’t necessarily trained to track without documentation from the oncology team. A written treatment summary and follow-up plan gives primary care providers what they need to monitor for the right things, rather than defaulting to general wellness checks that may miss cancer-specific risks entirely. What Should Survivorship Surveillance Actually Look Like? Surveillance protocols vary considerably depending on cancer type, stage, and treatment received, but generally include: Different cancer types have their own established follow-up guidelines for instance, breast, lung, colorectal, prostate, and melanoma each have distinct recommended surveillance schedules and tests, which is why a generic follow-up plan isn’t appropriate for every survivor. Is Emotional and Psychosocial Support Really Part of Medical Survivorship Care? Yes, this is explicitly built into formal survivorship guidelines, not an informal add-on. Consensus recommendations for follow-up care plans specifically call for addressing emotional and mental health, parenting, employment, financial issues, and insurance concerns, along with providing survivors with local and national resources to access appropriate support services. Many survivors experience anxiety around scans and follow-up appointments, sometimes called “scanxiety,” along with broader adjustment challenges — these are recognised, expected parts of the survivorship experience, not signs that something is wrong with how you’re coping. Please don’t dismiss ongoing physical or emotional symptoms as something you should simply push through. Persistent fatigue, pain, mood changes, or new symptoms should always be discussed with your care team rather than self-managed or ignored. What Can You Do to Support Your Own Survivorship? When Should You Contact Your Oncology Team? Build Your Personalised Survivorship Plan Remission is a milestone worth celebrating and survivorship care is how you protect the progress you’ve made. A structured, personalised plan gives you clarity on what to watch for and when to come back. Book a consultation with Dr. Namratha Sai Reddy to put together a survivorship care plan tailored to your diagnosis and treatment history. Frequently Asked Questions What is the

Can Obesity Increase Your Risk of Cancer? Here’s What Research Says
Yes. Obesity is now recognised as one of the most preventable risk factors for cancer, linked to at least13 different cancer types. It’s estimated to account for roughly 10% of all new cancer diagnoses in the United States each year, and up to half of certain cancers such as endometrial cancer. The good news is that this risk is not fixed. Sustained weight loss, whether through lifestyle change or bariatric surgery, has been shown to meaningfully lower cancer risk. An oncologist can help you understand your personal risk based on your weight history, family history, and other factors. Concerned about your cancer risk? Consult Dr. Namratha Sai Reddy for a personalised risk assessment and guidance on evidence-based prevention strategies. Key Takeaways When should you discuss weight and cancer risk with a doctor? If you have a BMI in the overweight or obese range and a family history of an obesity-linked cancer, or if you’re noticing unexplained symptoms such as abnormal bleeding, persistent digestive changes, or unexplained weight change, speak with a doctor rather than waiting for a routine check-up. Is the Link Between Obesity and Cancer Well Established? Yes, and the evidence has strengthened considerably over the past decade. Major international cancer-research bodies have concluded there is consistent evidence linking higher body fat to an increased risk of multiple cancers, based on reviews of well over a thousand studies. Large population studies covering millions of patients have found statistically significant associations between obesity and 13 cancer types, and researchers now project that in some countries, obesity may overtake smoking as the leading preventable cause of cancer within the next 15 years. How Many Cancers Are Actually Caused by Obesity? Estimates vary somewhat depending on the study, but they consistently point to a substantial public health burden. A major review found that obesity now accounts for roughly 10% of all new cancer diagnoses in the U.S. each year, and up to 50% of certain cancers such as endometrial and liver cancer. Other analyses put the overall figure lower, in the single digits, while some public-health estimates that include the full list of 13 linked cancer types put it considerably higher. The variation reflects differences in methodology, but the direction of the evidence is consistent. Can Obesity Cause Endometrial or Esophageal Cancer? Yes, these two cancers show the strongest obesity-related risk increases of any cancer type studied. What the Evidence Says For type 1 endometrial cancers, people with severe obesity have about seven times the risk, and those with overweight or obesity more broadly have two to four times the risk, compared with people at a healthy weight. For esophageal cancer, severe obesity is associated with nearly five times the risk, and obesity alone with more than double the risk. Can Obesity Cause Breast, Colorectal, Liver, or Kidney Cancer? Yes. These are among the most consistently reported obesity-linked cancers across studies, alongside pancreatic and gallbladder cancer. For breast cancer, the link is strongest after menopause — fat tissue produces an enzyme that converts other hormones into estrogen, and elevated estrogen exposure is a known driver of hormone-sensitive breast and endometrial cancers. For colorectal, liver, kidney, and pancreatic cancer, rising obesity rates among younger adults have specifically been associated with rising rates of these cancers being diagnosed at an earlier age than in previous decades. How Does Obesity Actually Cause Cancer? Obesity doesn’t cause cancer through a single mechanism, it reconfigures the body at a cellular level, creating conditions that make it easier for cancer to develop and spread. The main pathways researchers point to include: Does Losing Weight Actually Lower Cancer Risk? This is one of the most important and encouraging questions in this area of research, and the evidence, particularly from bariatric surgery studies increasingly says yes. What the Evidence Says A large study following patients after gastric bypass surgery found that bariatric surgery reduced overall cancer risk by 25% and cancer mortality by 43%, with even larger benefits in women. A separate large cohort study comparing more than 22,000 bariatric surgery patients to over 66,000 who didn’t have surgery found a33% lower risk of developing any cancer over 10 years of follow-up. More recent research adds an important nuance: the amount of weight lost matters, with greater weight loss associated with a further, dose-dependent reduction in cancer risk. Researchers believe part of this benefit comes from reduced estrogen levels following weight loss, which may particularly lower the risk of hormone-driven cancers such as breast and endometrial cancer. Most of this strongest evidence comes from bariatric surgery specifically; it remains less clear exactly how much cancer risk is reversed through non-surgical, intentional weight loss alone, though the underlying biological mechanisms would be expected to apply regardless of how the weight is lost. Does Obesity Affect Cancer Outcomes, Not Just Risk? Yes. Beyond increasing the chance of developing cancer in the first place, excess body fat is also associated with an approximately 17% increased risk of cancer-specific mortality once cancer has developed, underscoring that weight matters at every stage, not only before diagnosis. Does This Mean Everyone with Obesity Will Get Cancer? No. Obesity is a significant, well-documented risk factor — not a guarantee. Cancer risk is influenced by many factors working together, including genetics, family history, age, environmental exposures, and lifestyle. Many people with obesity never develop cancer, and people at a healthy weight can still be diagnosed. The point of this research is to identify a modifiable risk factor, not to suggest that body weight alone determines outcome. Please don’t use this information to self-diagnose risk or delay a medical evaluation for any symptoms you’re experiencing. A doctor can assess your full risk profile, not just your weight. What Can You Do to Lower Obesity-Related Cancer Risk? When Should You Consult a Doctor? Understand Your Personal Cancer Risk Obesity is one of the most significant, and most modifiable cancer risk factors we know of today. Whether your goal is prevention, early detection, or understanding how weight fits into your