

Key Takeaways: The first 30 days after a cancer diagnosis are often emotionally intense, but they are also one of the most important periods in your care journey. During this time, doctors gather detailed information about the disease, perform additional investigations, determine the stage of cancer, and create a personalised treatment plan. Contrary to what many people fear, treatment decisions are usually not made overnight. Cancer care today is highly specialised and carefully planned. The goal of the first month is to fully understand the cancer before beginning the most effective treatment approach. According to the World Health Organization (WHO), early diagnosis and timely treatment significantly improve cancer outcomes and survival rates worldwide. This guide explains what patients and families can realistically expect during the first 30 days after an oncology diagnosis. Why the First 30 Days Matter Hearing the words “you have cancer” can feel overwhelming. For many people, the first reaction after an oncology diagnosis is fear, confusion, and uncertainty about what comes next. Questions begin racing through the mind almost immediately: The first month after diagnosis is not just about treatment; it is about understanding the disease completely. Doctors use this time to determine: Modern oncology is highly personalised. Two patients with the same cancer type may receive completely different treatments depending on genetics, tumour biology, age, stage, and overall health. This is why careful evaluation during the early weeks is essential. Day 1–3: Processing the Diagnosis Emotionally The first few days after hearing a diagnosis are usually emotionally difficult. Patients commonly experience: Some people immediately search online for answers about: These emotional reactions are completely normal. Why Emotional Support Matters Early Research from the National Cancer Institute shows that emotional distress after diagnosis can affect sleep, appetite, concentration, and decision-making. This is why oncologists often encourage: The first few days are not the time to panic or assume the worst. Day 3–7: Understanding Your Exact Cancer Type Not all cancers behave the same way. One of the most important steps after an oncology diagnosis is identifying: Why This Matters Different cancers require completely different treatment approaches. For example: This is also when patients begin learning about the various types of cancer and symptoms associated with their disease. Common Cancer Features Doctors Evaluate Doctors assess several important cancer features, including: These details help create an accurate treatment plan. Day 5–10: Additional Tests Begin After diagnosis, additional investigations are often required before treatment starts. Patients are sometimes surprised that treatment does not begin immediately, but these tests are necessary to understand the disease fully. Common Tests Performed After Diagnosis Blood Tests Doctors check: Imaging Scans Scans help determine whether cancer has spread. Common imaging studies include: Biopsy Review In many cases, pathology samples are reviewed again to confirm diagnosis accuracy. Molecular or Genetic Testing Some cancers require advanced testing to identify mutations that may respond to targeted therapies. Understanding the Importance of a “Test to Check for Cancer” Many patients ask whether there is one universal test to check for cancer. The answer is no. A cancer diagnosis usually involves multiple investigations because each cancer behaves differently. According to the American Cancer Society, a cancer diagnosis may involve imaging, biopsies, laboratory testing, endoscopy, and molecular analysis, depending on the cancer type. Why Multiple Tests Are Necessary Doctors need to understand: These tests help avoid unnecessary or ineffective treatments. Day 7–14: Meeting the Oncology Team Cancer care today is multidisciplinary. This means patients may meet: Each specialist contributes to the treatment strategy. What Happens During These Consultations? Doctors explain: This is also the time when patients should ask questions freely. Questions Patients Should Ask During the First Two Weeks Patients often feel overwhelmed and forget important questions during appointments. Helpful questions include: Clear communication helps patients feel more confident and informed. Day 10–20: Creating a Personalised Treatment Plan Once all investigations are complete, the oncology team develops an individualised treatment strategy. Possible Treatment Options Depending on the cancer type and stage, treatment may include: Many patients ask: is there a treatment for cancer that guarantees a cure? The answer depends on: Many cancers today are highly treatable, especially when detected early. Understanding How Cancer Happens Patients often blame themselves after diagnosis and search for explanations about how cancer happens. Cancer develops when abnormal cells begin growing uncontrollably due to genetic damage or mutations. Common Factors Linked to Cancer Development Some major contributors include: However, in many patients, there may not be a single identifiable main reason for cancer. Cancer is usually caused by a combination of factors over time. According to the National Cancer Institute, most cancers develop because of interactions between genetics, lifestyle, and environmental exposures. Day 15–25: Preparing Physically and Mentally for Treatment Once treatment plans are finalised, preparation begins. Patients may undergo: Why Preparation Matters Proper preparation can: Mental preparation is equally important. Counselling and support groups often help patients manage fear and uncertainty before treatment starts. Recognising Common Cancer Symptoms Different cancers produce different symptoms, but certain warning signs appear more commonly. Common Cancer Symptoms May Include: Because many types of cancer and symptoms overlap with less serious illnesses, medical evaluation is essential. Ignoring a persistent cancer symptom may delay diagnosis. Day 20–30: Starting Treatment For many patients, treatment begins during the third or fourth week after diagnosis. The timing depends on: What Patients Often Feel Before Treatment Common emotions include: These feelings are completely understandable. Modern oncology teams now focus heavily on: Important Statistics About Early Cancer Care Early Detection Improves Survival The World Health Organization states that many cancers have a high chance of cure if diagnosed early and treated appropriately. Cancer Is Increasing Worldwide According to the International Agency for Research on Cancer (IARC): The First Month Is About Clarity, Not Panic The first 30 days after a cancer diagnosis can feel emotionally exhausting, but they are also one of the most important phases of care. This period allows doctors to understand the disease completely, evaluate all available treatment options, and

10 Cancer Myths Your Doctor Wants You to Stop Believing
Key Takeaways Cancer remains one of the most feared diseases globally, but also one of the most misunderstood. Despite major advancements in medicine, myths and misinformation about cancer continue to spread through social media, internet forums, WhatsApp forwards, and word-of-mouth advice. These misconceptions are not harmless. False beliefs about cancer often delay screenings, discourage treatment, increase stigma, and create unnecessary fear among patients and families. According to the World Health Organization (WHO), cancer accounted for nearly 10 million deaths worldwide, making it one of the leading causes of death globally. At the same time, survival rates for many cancers have improved dramatically because of early detection and advances in treatment. Understanding the truth behind common cancer myths can help people make informed healthcare decisions and avoid dangerous misinformation. Why Cancer Myths Are So Harmful Fear creates confusion and confusion creates myths. When people hear the word “cancer,” they often search online for answers about: Unfortunately, many online sources promote misleading or scientifically inaccurate claims. The National Cancer Institute (NCI) warns that false information about cancer can “hinder good prevention and treatment decisions. Myth 1: Cancer Is Always a Death Sentence Fact: Many cancers today are treatable and many are curable. One of the oldest general myths about cancer is that every diagnosis automatically leads to death. This belief is outdated. Modern oncology has transformed cancer care through: According to the American Cancer Society Cancer Statistics Report, nearly 70% of people diagnosed with cancer now survive at least five years after diagnosis — a dramatic improvement compared to previous decades. The National Cancer Institute’s Cancer Myths Page also reports that five-year survival rates for cancers like breast, prostate, and thyroid cancer are now above 90% in many cases. Why This Myth Is Dangerous Believing cancer is always fatal may cause people to: A cancer diagnosis today is not the same as it was 20 or 30 years ago. Myth 2: Cancer Is Contagious Fact: No, is cancer contagious? Absolutely not. You cannot get cancer from: This misconception creates unnecessary isolation and emotional distress for patients. The National Cancer Institute clearly states that cancer does not spread from person to person like infections such as flu or COVID-19. Then Why Are People Confused? Certain infections can increase cancer risk, including: However, the infection may spread not the cancer itself. So when people ask whether cancer can be transmitted, the answer is generally no. Myth 3: Sugar Feeds Cancer and Eliminating Sugar Can Cure It Fact: All cells use glucose, not just cancer cells. This is one of the most widespread cancer myths and facts debates online. Cancer cells do consume glucose for energy, but so do: Completely eliminating sugar does not “starve” cancer. What Research Actually Shows The stronger link is between: The World Health Organization Cancer Fact Sheet states that high body mass index, low fruit and vegetable intake, alcohol use, and inactivity contribute significantly to cancer risk worldwide. Extreme diets during cancer treatment may weaken immunity and worsen nutritional health. Myth 4: If Nobody in Your Family Had Cancer, You Won’t Get It Fact: Most cancers are not inherited. Many people wrongly assume that family history is the only reason cancer develops. According to the National Cancer Institute, only about 5–10% of cancers are linked to inherited genetic mutations. The remaining majority occur due to aging, lifestyle, environmental exposure, and random genetic mutations over time. Common Examples of Stuff That Causes Cancer This is why even healthy people with no family history may occasionally develop cancer. Myth 5: Surgery or Biopsy Makes Cancer Spread Fact: Biopsies and surgeries are critical for diagnosis and treatment. This is one of the most dangerous cancer myths vs facts misunderstandings because it may stop patients from seeking treatment. The National Cancer Institute Cancer Myths Page explains that the chances of surgery or biopsy causing cancer spread are extremely low. Surgeons use specialized techniques to prevent tumor cell spread during procedures. Why Biopsies Matter Biopsies help doctors: Without biopsy confirmation, effective treatment planning becomes difficult. Myth 6: Mobile Phones and Microwaves Cause Cancer Fact: There is currently no strong evidence proving normal use directly causes cancer. People often fear everyday technology because radiation sounds dangerous. However, microwaves and cell phones use non-ionizing radiation, which differs from harmful ionizing radiation like X-rays. The National Cancer Institute notes that many commonly feared causes of cancer have not been scientifically proven. What Actually Raises Risk More Scientifically established risk factors include: Understanding real risks matters far more than believing viral internet myths. Myth 7: Positive Thinking Alone Can Cure Cancer Fact: Emotional strength helps — but medical treatment is essential. Mental wellbeing absolutely matters during cancer care. Emotional support can improve: However, positive thinking alone cannot eliminate cancer cells. Modern Cancer Care Is Multifaceted Today’s treatment may include: Patients do better when emotional support works alongside evidence-based treatment. Myth 8: If You Feel Fine, You Don’t Have Cancer Fact: Many cancers have no symptoms early on. People frequently search online for how to know if you have cancer, but early-stage cancer is often silent. According to the World Health Organization, many cancers can be successfully treated if detected early. Some Early Cancers That May Have Few Symptoms Warning Signs That Should Never Be Ignored Early medical evaluation saves lives. Myth 9: Cancer Always Spreads Quickly Fact: Every cancer behaves differently. One of the biggest fears after diagnosis is whether does cancer spread immediately. The truth is that cancer behavior depends on: Some cancers grow slowly over years, while others may progress faster. The World Health Organization Cancer Overview explains that metastasis — the spread of cancer to other organs — is a defining feature of cancer, but the speed and pattern vary greatly between cancer types. Examples This is why individualized treatment planning is essential. Myth 10: Cancer Treatment Is Always Worse Than Cancer Itself Fact: Modern treatments are safer and more personalized than ever before. Fear of chemotherapy side effects prevents many patients from seeking treatment.

Understanding Chemotherapy Side Effects and How to Manage Them
Chemotherapy remains one of the most widely used treatments for cancer. It works by destroying rapidly dividing cancer cells and preventing them from growing and spreading. While chemotherapy can be highly effective in controlling cancer, it may also affect healthy cells that divide quickly, leading to chemotherapy side effects. Understanding what are the side effects of chemotherapy and learning how to manage them can help patients cope better during treatment. With proper medical care and supportive therapies, many cancer chemotherapy side effects can be controlled or reduced. Key Takeaways What Are the Side Effects of Chemotherapy? Chemotherapy side effects occur because chemotherapy drugs attack rapidly dividing cells in the body, including both cancer cells and some healthy cells. When healthy cells in areas such as the bone marrow, digestive tract, and hair follicles are affected, patients may experience various symptoms during treatment. To answer what are the side effects of chemotherapy, the effects can range from mild discomfort to more noticeable physical changes, depending on the type of drug used and the patient’s overall health. These chemotherapy treatment side effects vary from person to person. Some patients may experience only mild symptoms, while others may experience several common side effects of chemotherapy during treatment cycles. Most symptoms are temporary and improve after treatment ends. Research from the U.S. National Cancer Institute notes that chemotherapy affects healthy cells but many of these cells recover after treatment is completed. Why Do Chemotherapy Side Effects Occur? Chemotherapy side effects occur because chemotherapy drugs cannot always distinguish between cancer cells and healthy cells that divide quickly. As a result, some normal tissues are temporarily affected during treatment. These cancer chemotherapy side effects commonly occur in tissues with rapid cell turnover, including hair follicles, digestive tract lining, and bone marrow. Cells most affected by chemotherapy include: Damage to these cells leads to many common side effects of chemotherapy, such as hair loss, fatigue, anaemia, and digestive discomfort. According to the American Cancer Society, side effects depend on the type of drug, dosage, and length of treatment. What Are the Common Side Effects of Chemotherapy? The common side effects of chemotherapy vary depending on the medications used and the patient’s overall health. While not everyone experiences all symptoms, several side effects occur frequently during chemotherapy treatment. Common chemotherapy side effects include: Understanding what are the side effects of chemotherapy helps patients prepare for treatment and seek timely medical support when symptoms appear. Research suggests that fatigue is among the most frequently reported cancer chemotherapy side effects, affecting up to 80% of patients undergoing chemotherapy. Chemotherapy vs Radiation Side Effects: What Is the Difference? Understanding chemotherapy vs radiation side effects is important because these two cancer treatments affect the body in different ways. Chemotherapy circulates throughout the bloodstream and can affect many parts of the body, while radiation therapy targets a specific area. Key differences in chemotherapy vs radiation side effects Chemotherapy Radiation therapy Because chemotherapy acts throughout the body, cancer chemotherapy side effects may appear more widespread than radiation-related symptoms. What Are the Long-Term Chemotherapy Treatment Side Effects? While most chemotherapy treatment side effects are temporary, some patients may experience long-term or late effects depending on the drugs used and the duration of treatment. Certain chemotherapy drugs can affect organs such as the heart, nerves, or kidneys if used at high doses or over long periods. Possible long-term chemotherapy side effects Although these complications are less common, doctors monitor patients carefully during treatment to detect early signs of long-term cancer chemotherapy side effects. How Can Chemotherapy Side Effects Be Managed? Managing chemotherapy side effects is an essential part of cancer care. Doctors often prescribe supportive medications and recommend lifestyle adjustments to help patients cope with treatment. Many chemotherapy side effects can be reduced with early intervention and supportive care. Ways to manage chemotherapy treatment side effects Supportive care strategies have improved significantly over the years, allowing doctors to manage many common side effects of chemotherapy more effectively. According to the World Health Organization, supportive therapies play an important role in improving the quality of life for cancer patients undergoing treatment. When Should Patients Report Chemotherapy Side Effects to Their Doctor? Patients should inform their doctor whenever chemotherapy side effects become severe, persistent, or interfere with daily activities. Early medical attention can help prevent complications and improve comfort during treatment. Some symptoms require immediate medical attention, especially if they indicate infection or severe reactions. Symptoms that should be reported immediately Prompt reporting helps doctors adjust treatment plans and manage chemotherapy ke side effect symptoms safely. Living Well During Chemotherapy Understanding what are the side effects of chemotherapy allows patients to prepare mentally and physically for treatment. While chemotherapy treatment side effects can be challenging, modern supportive care has made it possible for many patients to continue daily activities during treatment. Advances in cancer medicine are also improving the management of cancer chemotherapy side effects, helping patients maintain a better quality of life throughout their cancer journey. With proper medical guidance, nutrition, emotional support, and symptom management, many patients successfully navigate chemotherapy while continuing their path toward recovery. FAQs 1. What are the side effects of chemotherapy? Chemotherapy side effects may include fatigue, nausea, hair loss, mouth sores, and increased risk of infections. 2. Why do chemotherapy side effects occur? Cancer chemotherapy side effects occur because chemotherapy drugs affect both cancer cells and rapidly dividing healthy cells. 3. What are the most common side effects of chemotherapy? The common side effects of chemotherapy include fatigue, nausea, hair loss, and lowered immunity. 4. Are chemotherapy side effects permanent? Most chemotherapy treatment side effects are temporary and improve after treatment ends. 5. What is the difference between chemotherapy vs radiation side effects? In chemotherapy vs radiation side effects, chemotherapy affects the entire body while radiation side effects occur mainly in the treated area. 6. Can chemotherapy side effects be prevented? While not all chemotherapy ke side effects can be prevented, many can be reduced with supportive medications. 7. How
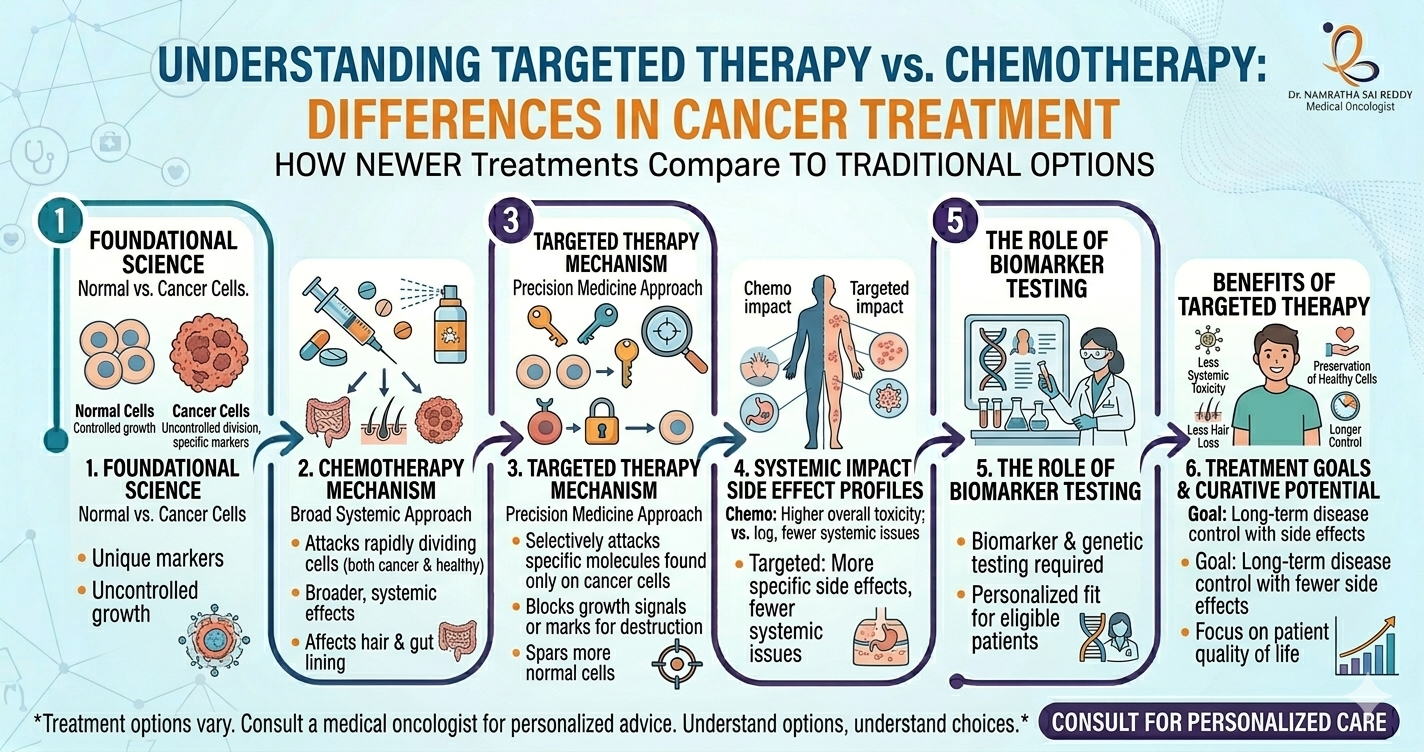
Understanding Targeted Therapy in Cancer Treatment: How It Differs from Chemotherapy
Cancer treatment is rapidly evolving with the development of precision medicine. Traditional treatments, such as chemotherapy, attack rapidly dividing cells across the body, but newer approaches focus on the biological mechanisms that drive cancer growth. One of the most important advances in modern oncology is targeted therapy, which allows doctors to treat cancer by attacking specific genetic mutations or proteins in cancer cells. Understanding what is targeted therapy in cancer, how it works, and how targeted therapy vs chemotherapy differs from chemotherapy can help patients better understand modern cancer treatment options. Key Takeaways What Is Targeted Therapy in Cancer? Targeted therapy is a type of cancer treatment that uses drugs designed to attack specific molecular targets involved in cancer growth and survival. To understand what is targeted therapy in cancer, it is important to know that many cancers develop due to genetic mutations that activate abnormal proteins or signalling pathways. Unlike traditional chemotherapy, targeted therapy for cancer focuses on the biological mechanisms that allow cancer cells to grow, divide, and spread. These therapies may block proteins that signal cancer cells to grow, interfere with blood vessel formation that feeds tumours, or trigger cancer cell death. Advances in genomic testing have helped identify many actionable targets, enabling doctors to design personalised treatment strategies based on the molecular profile of each tumour. How Does Targeted Therapy Work? Targeted therapy works by interfering with specific molecules or pathways that cancer cells depend on for survival. These targets may include proteins on the cell surface, enzymes inside the cell, or genetic mutations that drive uncontrolled growth. Once these targets are identified, targeted therapy for cancer uses drugs designed to block them and stop cancer progression. Key ways targeted therapy works: Research shows that patients receiving matched targeted therapies often experience improved overall survival and progression-free survival compared with patients who do not receive targeted treatments. Targeted Therapy vs Chemotherapy: What Is the Difference? The difference between targeted therapy vs chemotherapy lies mainly in precision and mechanism of action. Chemotherapy works by destroying rapidly dividing cells throughout the body, which includes cancer cells but also healthy cells such as hair follicles and cells in the digestive tract. In contrast, targeted therapy vs chemotherapy involves drugs designed to attack specific molecular abnormalities found in cancer cells. Key differences in targeted therapy vs chemotherapy Chemotherapy Targeted therapy Studies in patients with metastatic renal cell carcinoma have shown that targeted treatments improved survival rates compared with non-targeted therapies, with higher survival percentages at 1-, 2-, and 3-year follow-ups. Targeted Therapy vs Immunotherapy: How Are They Different? The difference between targeted therapy vs immunotherapy lies in how the treatments fight cancer. Targeted therapy directly blocks molecules that cancer cells need to grow, while immunotherapy works by stimulating the immune system to recognise and destroy cancer cells. Both therapies are considered forms of precision medicine, but they operate through different biological mechanisms. Understanding targeted therapy vs immunotherapy Targeted therapy Immunotherapy Research suggests that combining targeted therapy with immunotherapy may further improve survival outcomes in certain cancers, such as liver cancer. What Are the Possible Targeted Therapy Side Effects? Although targeted therapy is designed to be more precise, patients can still experience targeted therapy side effects because some targeted pathways also exist in normal cells. These side effects vary depending on the drug and the biological pathway being targeted. Common targeted therapy side effects Studies evaluating targeted drugs in certain cancers have shown that while side effects may occur more frequently than with a placebo, they are generally manageable with proper monitoring and supportive care. What Is the Targeted Therapy Success Rate? The targeted therapy success rate depends on several factors, including cancer type, genetic mutation, stage of disease, and patient health. In cancers with identifiable molecular drivers, targeted treatments have significantly improved survival outcomes. For example, research in advanced non-small cell lung cancer showed that patients receiving targeted therapy had a median overall survival of about 45 months compared with 17 months for chemotherapy alone, demonstrating a substantial improvement. Factors influencing the targeted therapy success rate These results highlight how targeted therapy for cancer can dramatically improve treatment outcomes when the correct molecular target is identified. When Do Doctors Recommend Targeted Therapy? Doctors recommend targeted therapy for cancer when genetic or biomarker testing reveals specific molecular targets that can be treated with targeted drugs. This approach is an important part of precision oncology. Situations where targeted therapy may be recommended With advances in genomic sequencing and biomarker testing, doctors can increasingly tailor treatment strategies to the individual characteristics of each patient’s cancer. Why Is Targeted Therapy Considered a Breakthrough in Cancer Treatment? Targeted therapy is considered a breakthrough because it shifts cancer treatment from a generalised approach to a personalised one. Instead of broadly destroying cells, the therapy focuses on the molecular drivers responsible for tumour growth. Reasons targeted therapy for cancer is revolutionary With ongoing research and development, new targeted drugs continue to expand treatment possibilities for patients with previously difficult-to-treat cancers. Moving Toward Personalised Cancer Care Understanding what is targeted therapy in cancer, the differences between targeted therapy vs chemotherapy, and the role of targeted therapy vs immunotherapy helps patients better navigate modern cancer care. As research continues to uncover new molecular targets, targeted therapy is expected to play an even larger role in oncology. This approach represents one of the most important steps toward precision medicine—delivering treatments that are tailored to the unique biology of each patient’s cancer. FAQs 1. What is targeted therapy in cancer? Targeted therapy is a cancer treatment that attacks specific genes, proteins, or molecular pathways that allow cancer cells to grow. 2. How is targeted therapy different from chemotherapy? In targeted therapy vs chemotherapy, targeted therapy focuses on specific cancer cell mechanisms, while chemotherapy attacks all rapidly dividing cells. 3. Is targeted therapy used for all cancers? No. Targeted therapy for cancer works best when the tumour contains specific genetic mutations or molecular targets. 4. What are common targeted therapy side effects?
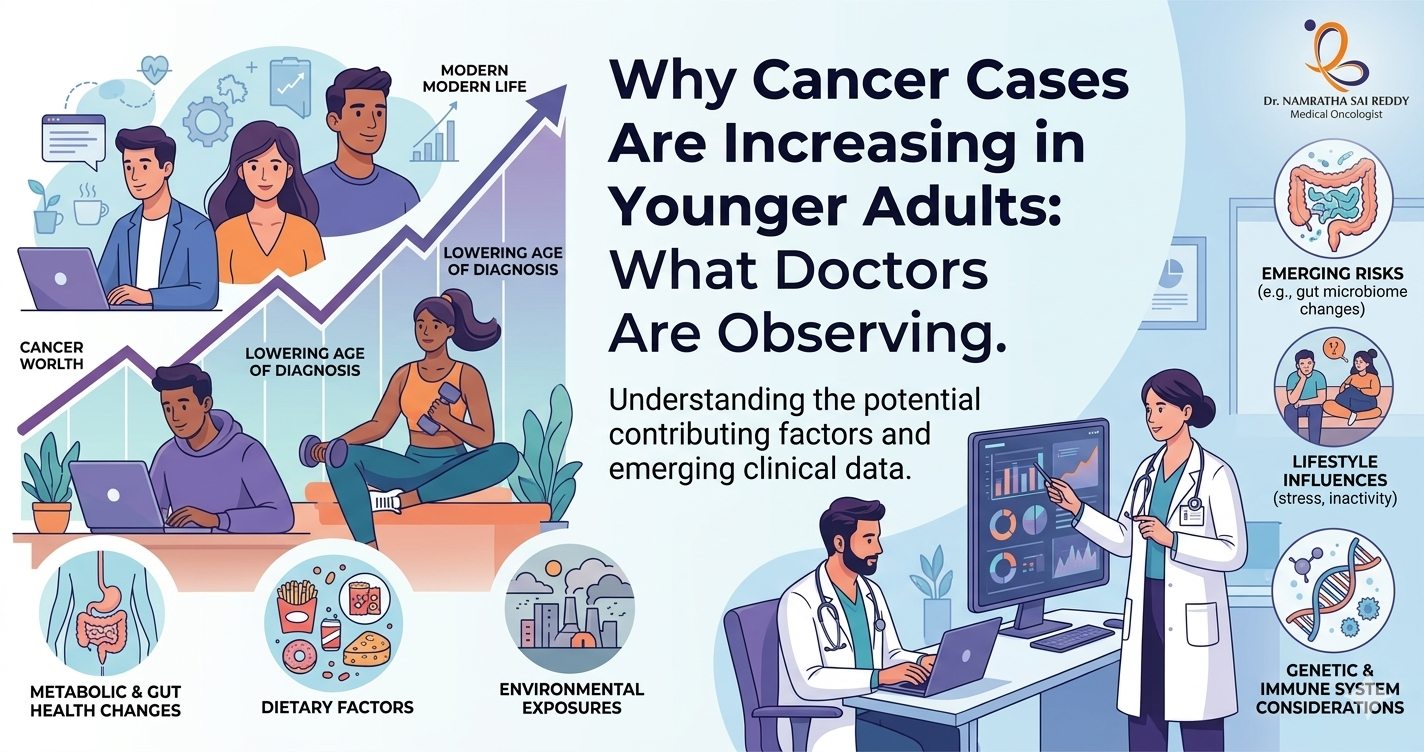
Why Cancer Cases Are Increasing in Younger Adults: What Doctors Are Observing
Cancer has traditionally been considered a disease that primarily affects older adults. However, doctors across the world are increasingly observing a shift in this pattern. More people in their 20s, 30s, and 40s are being diagnosed with cancer compared with previous decades. This emerging trend has raised important questions about lifestyle changes, environmental exposure, and evolving health patterns. In India as well, oncologists and physicians are noticing a gradual rise in cancer cases in India, particularly among younger individuals. While improved detection and awareness play a role, researchers believe several additional factors may be contributing to the increase. According to the World Health Organization, cancer remains one of the leading causes of death globally. Meanwhile, data from the International Agency for Research on Cancer estimates that over 1.4 million new cancer diagnoses occur annually in India, highlighting the growing burden of cancer cases in India. Key Takeaways Are Cancer Diagnoses Increasing in Younger Adults? Doctors worldwide are reporting more cancer diagnoses in people under 50. Research suggests early-onset cancers are rising globally, making awareness and early screening increasingly important for younger populations. Key statistics These findings confirm that cancer cases increasing among younger populations is becoming an important global health concern. Why Are Doctors Seeing More Cancer Cases in Young Adults? Multiple factors, such as lifestyle changes, environmental exposures, obesity, dietary habits, and genetic influences, may contribute to rising cancer diagnoses in younger adults across many countries. There is no single explanation for why cancer cases are increasing in India and globally. Instead, researchers believe several interconnected factors may be contributing to the rise. Lifestyle changes Modern lifestyles have changed dramatically over the past few decades. Possible risk factors include: These lifestyle shifts may affect metabolism, hormones, and inflammation, potentially influencing cancer risk. Environmental exposures Environmental factors are also being studied as possible contributors to the increase in cancer cases. Possible exposures include: Rapid urbanisation and environmental changes may influence long-term health risks. Which Types of Cancer Are Increasing in Younger Adults? Several cancers, including breast, colorectal, thyroid, and stomach cancers, are being diagnosed more frequently in younger adults, suggesting that early-onset cancer trends are affecting multiple organs. Doctors are observing increasing rates of several cancer types in younger populations. Common cancers seen in younger adults Breast cancer One of the most notable trends is the rise in breast cancer cases in India, particularly among women under 45. Some hospital-based studies in India suggest that a significant proportion of breast cancer patients are younger than 50, which is higher than in several Western countries. Colorectal cancer Colorectal cancer is increasingly being diagnosed in people under 50 in many parts of the world. Thyroid cancer Improved detection partly explains rising cases, but real increases may also exist. Gastrointestinal cancers Some studies suggest increases in stomach and pancreatic cancers among younger individuals. These trends highlight why understanding why cancer cases are increasing in India is becoming increasingly important. Is Better Detection Responsible for Rising Cancer Numbers? Improved screening and diagnostic technologies have increased the detection of cancers earlier, but experts believe better detection alone cannot fully explain the rising number of diagnoses. Modern medicine now includes: Because of these improvements, some cancer cases that might previously have gone undetected are now diagnosed earlier. However, researchers believe that detection improvements do not fully explain why cancer cases increasing worldwide. Lifestyle and environmental changes likely play a significant role. Why Is Breast Cancer Increasing in Younger Women? Hormonal changes, lifestyle factors, delayed pregnancies, obesity, and genetic predisposition may contribute to rising breast cancer cases in India, especially among women under the age of 45. Possible contributing factors Hormonal influences Changes in reproductive patterns, such as delayed childbirth, may influence hormonal exposure. Lifestyle changes Risk factors include: Genetic factors Family history and inherited genetic mutations may increase risk in some individuals. Because of these trends, doctors emphasise awareness of breast health and early evaluation of symptoms. What Symptoms Should Younger Adults Watch For? Persistent symptoms such as unexplained weight loss, unusual lumps, prolonged fatigue, or abnormal bleeding should never be ignored and should be evaluated by a doctor promptly. One challenge with rising cancer cases in India is that younger individuals often assume they are too young to develop cancer. However, early medical evaluation is essential. Symptoms that should not be ignored Recognising these warning signs early can lead to timely diagnosis and more effective treatment. How Can Younger Adults Reduce Cancer Risk? Adopting healthy lifestyle habits, maintaining a balanced diet, exercising regularly, avoiding tobacco, limiting alcohol, and undergoing recommended health screenings can help reduce cancer risk. While not all cancers are preventable, several lifestyle changes may help reduce risk. Preventive measures include Public awareness about why cancer cases are increasing in India is essential to encourage healthier lifestyle choices. Take Early Symptoms Seriously and Prioritise Preventive Care The rising number of cancer cases in India and globally highlights the need for greater awareness and proactive health management. As doctors observe cancer cases increasing among younger adults, early detection and preventive strategies are becoming more important than ever. Understanding why cancer cases are increasing in India can help individuals make informed health decisions and encourage early medical consultation when symptoms appear. By maintaining healthy lifestyles, staying aware of warning signs, and seeking timely medical care, individuals can significantly improve their chances of early diagnosis and successful treatment. Frequently Asked Questions (FAQs) 1. Are cancer cases increasing among younger adults? Yes, studies worldwide show a growing number of early-onset cancers in people under 50, highlighting the importance of awareness and early medical evaluation. 2. Why are cancer cases increasing globally? Researchers believe lifestyle changes, environmental exposures, obesity, and improved detection methods all contribute to rising cancer cases. 3. Are cancer cases in India increasing? Yes, healthcare data suggests a steady rise in cancer cases in India, with more diagnoses being reported each year. 4. Why are breast cancer cases in India rising? Factors such as lifestyle changes, hormonal influences, delayed pregnancies, and genetic predisposition may
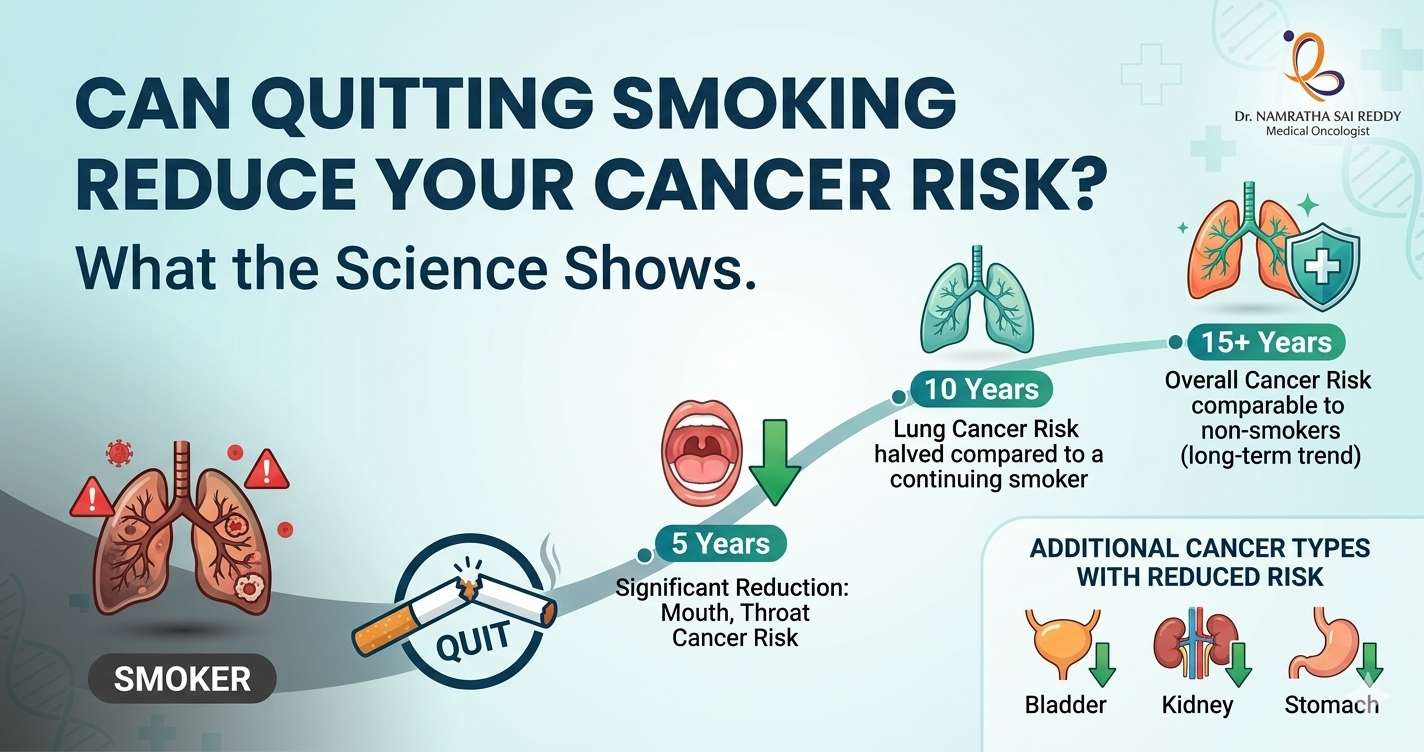
Can Quitting Smoking Reduce Your Cancer Risk? What the Science Shows
Yes, quitting smoking significantly reduces cancer risk at any age. People who quit completely have a 17% lower overall cancer risk than those who continue smoking. Lung cancer risk alone drops by up to 57% for those who quit before age 50, and by 39% for those who quit after 50. Benefits begin within months and compound the longer you stay smoke-free. Key Takeaways Smoking remains one of the leading causes of preventable cancer worldwide. While the dangers of tobacco are well known, many smokers believe that once the damage is done, quitting may not make much difference. Research shows the opposite: quitting smoking at any age significantly reduces cancer risk. The body begins to recover sooner than many people expect, and the most dramatic improvements appear in lung cancer risk. The Link Between Smoking and Cancer Smoking exposes every cell in your body to a barrage of harmful chemicals. According to the American Cancer Society, tobacco smoke contains more than 7,000 chemicals, including at least 70 known carcinogens. These compounds damage DNA, trigger chronic inflammation, and impair the body’s natural ability to repair cells. Tobacco use is strongly associated with multiple cancers, including: • Lung cancer • Liver cancer • Colorectal cancer • Stomach cancer • Bladder cancer • Pancreatic cancer What Research Says About Quitting Smoking A landmark study published in JAMA Network Open analysed health data from nearly 3 million adults over age 30, with an average follow-up period of 13 years. Researchers found that people who quit smoking completely had a 17% lower overall cancer risk compared with those who continued to smoke. The risk reduction varied across different types of cancer: • 42% lower risk of lung cancer • 27% lower risk of liver cancer • 20% lower risk of colorectal cancer • 14% lower risk of stomach cancer Among these, lung cancer risk showed the fastest decline after quitting. Lung Cancer Risk Drops Faster Than Many Expect A long-term analysis from the Framingham Heart Study examined nearly 9,000 participants over a period of 25 to 34 years. The study revealed several important findings: • Nearly 93% of lung cancer cases occurred in heavy smokers. • Within five years of quitting, the risk of lung cancer dropped by about 39% compared with current smokers. • The risk continued to decline the longer someone remained smoke-free. A complementary 2024 study in the Journal of the National Cancer Institute, which tracked over 24,600 Finnish male smokers from 1985 to 2012, confirmed that even simply reducing cigarettes per day lowers lung cancer risk, though completely quitting remains the most effective strategy. However, researchers at CA: A Cancer Journal for Clinicians note that even decades after quitting, former heavy smokers (20+ pack-years) may retain a meaningfully elevated lung cancer risk compared with lifelong non-smokers, underscoring the importance of continued screening. Does Age Matter When You Quit? While quitting at any age offers real benefits, the earlier you stop, the greater the protection. Research reported by Medical News Today and drawn from the JAMA Network Open study shows: The message is clear: it is never too late to quit. Every smoke-free year translates into a measurable reduction in cancer risk. Why Cancer Risk May Appear Higher Shortly After Quitting Some studies have observed a temporary increase in cancer diagnoses within the first few years after quitting. This can seem confusing, but researchers believe it is largely due to what is known as the “sick quitter effect”. In some cases, individuals stop smoking because they are already experiencing early symptoms of illness. As a result, diagnoses may occur shortly after quitting, making it appear as though risk has increased. When researchers account for this factor, the overall trend shows a steady decline in cancer risk following smoking cessation. Health Improvements Begin Quickly After Quitting The body begins repairing itself almost immediately. Here is what research, including findings summarised by the American Cancer Society, shows about the recovery trajectory: Heart rate begins to return to normal levels. Carbon monoxide levels in the blood drop significantly, improving oxygen delivery to cells. Lung function and circulation improve noticeably. Respiratory symptoms like coughing and shortness of breath diminish. Lung cancer risk drops by approximately 39% compared with current smokers (Framingham Heart Study). The risk of several other cancers also begins to fall. Overall cancer risk approaches, though may not fully equal that of lifelong non-smokers, particularly for heavy former smokers. Screening Remains Important for Former Smokers A systematic review published in CA: A Cancer Journal for Clinicians (2023) found that lung cancer risk may remain meaningfully elevated for two to three decades in former heavy smokers, even beyond the 15-year cut-off that currently defines US screening eligibility. The authors argue that age-based screening criteria may be more appropriate than time-since-quitting criteria. Current US Preventive Services Task Force guidelines recommend annual low-dose CT lung cancer screening for adults aged 50 to 80 who have a 20-pack-year smoking history and currently smoke or have quit within the past 15 years. Former heavy smokers should speak with their doctor about continued eligibility. It Is Never Too Late to Quit The evidence is clear. Quitting smoking dramatically reduces cancer risk, and the benefits begin much sooner than most people realise. Even for long-term smokers, stopping today can lead to measurable health improvements within just a few years. While former smokers may still benefit from cancer screening and medical follow-up, the long-term advantages of quitting far outweigh the risks of continuing. Every smoke-free year helps your body heal and lowers your chances of developing cancer. FAQs How soon does cancer risk drop after quitting?Cancer risk begins to decline within a few years, with lung cancer risk dropping significantly within about five years. Is it worth quitting after age 50?Yes. Quitting
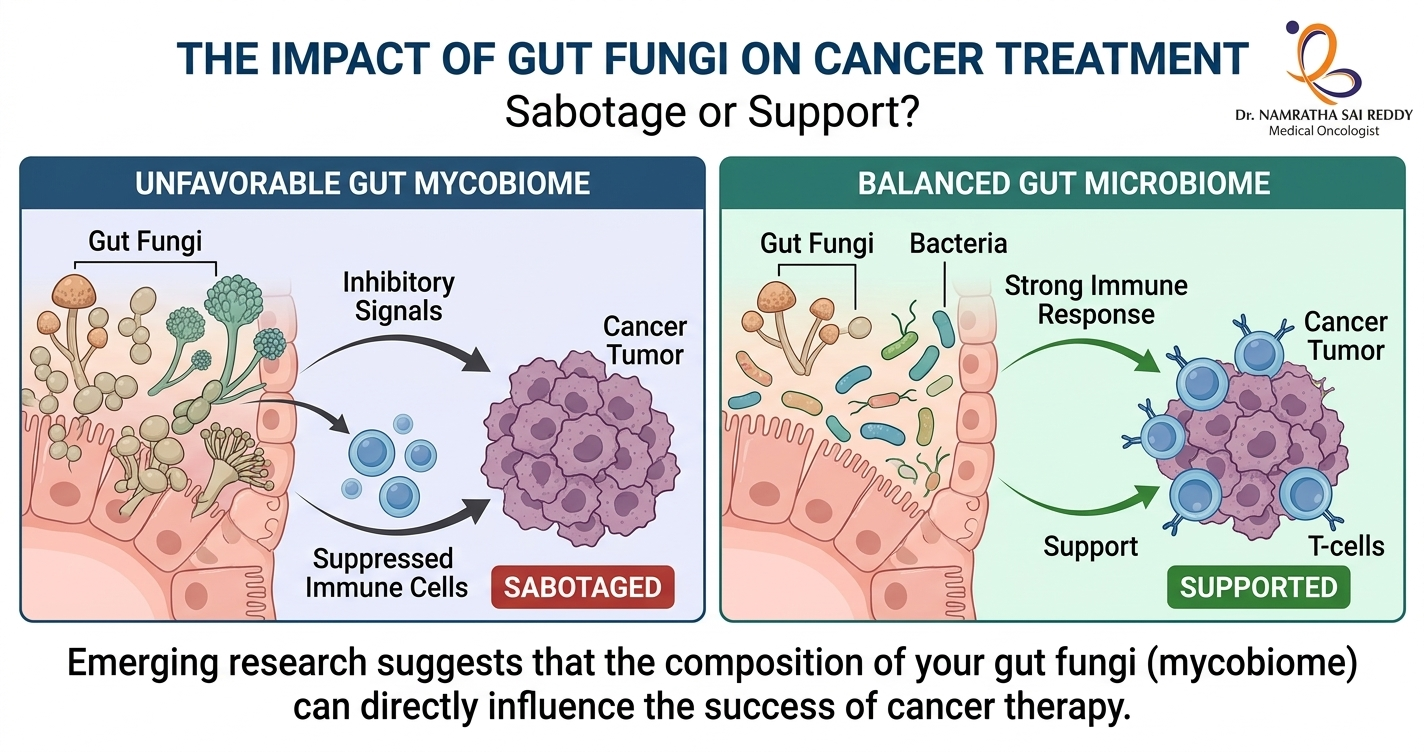
Can Gut Fungi Affect Your Cancer Treatment? What the Science Says
Yes, gut fungi can affect cancer treatment outcomes. Research published in Cancer Cell by scientists at Cedars-Sinai Medical Centre found that intestinal fungi suppress anti-tumour immune responses after radiation therapy. Fungal overgrowth, which frequently follows antibiotic use, was shown to reduce treatment effectiveness in models of both breast cancer and melanoma. Treating the animals with antifungal drugs restored the immune response and improved outcomes. Scientists now believe the gut mycobiome may be one of the missing pieces explaining why only 20 to 40% of patients respond to immunotherapy. Key Takeaways What Is the Gut Mycobiome? The human gut hosts approximately 38 trillion microorganisms, including bacteria, fungi, viruses, and other microbes. While research has traditionally focused on bacteria, the gut’s fungal community (the mycobiome) is now attracting serious scientific attention. Fungi make up just 0.01 to 2% of cells in the gut microbiome, but researchers have reliably identified 50 to 100 fungal genera living there. These fungi colonise early in life through birth, breastfeeding, food intake, and environmental exposure. Under normal conditions, they are non-pathogenic. However, when bacterial populations decline or the immune system is disrupted, fungal communities can shift dramatically, with serious downstream effects on immunity and treatment response. The Cedars-Sinai Study: Fungi and Radiation Therapy The most significant study in this field to date was led by Dr. Stephen Shiao and Dr. David Underhill at Cedars-Sinai Medical Centre. Published in Cancer Cell, the research found that intestinal bacteria and fungi have directly opposing effects on anti-tumour immune responses following radiation therapy. Consistent results were observed across both breast cancer and melanoma models, suggesting the findings may apply broadly across cancer types. Key findings: This is clinically relevant because antibiotics are routinely prescribed to cancer patients who are at elevated infection risk. The study suggests that this common practice may, in some cases, inadvertently compromise treatment outcomes by promoting fungal overgrowth. The Dectin-1 Connection: How Tumours Sense Fungi A key discovery from the Cedars-Sinai research was the role of a fungal-sensing immune receptor called Dectin-1. This protein detects beta-1,3-glucan, a compound in fungal cell walls, and activates the body’s antifungal immune pathways. It is primarily expressed in macrophages and dendritic cells within tumours. Using data from The Cancer Genome Atlas, the researchers found: As the National Cancer Institute noted in its coverage of the study, Dectin-1 could serve as a biomarker to identify patients with an unfavourable microbiome composition ahead of treatment. Specific Fungi Linked to Cancer Risk A comprehensive review published in Gut Microbes (2025) highlights specific fungal species now linked to distinct cancer outcomes: The review also notes that in cancer patients, the gut mycobiome undergoes substantial remodelling in both its composition and ecological structure. These shifts are increasingly recognised as important modulators of disease progression, immune dynamics, and responsiveness to therapy. How Gut Fungi Influence Immunotherapy Immunotherapy works by activating immune cells to recognise and destroy cancer. Research published in npj Biofilms and Microbiomes (2025) outlines the key mechanisms through which gut fungi influence this process. Immune signalling modulation – Fungal molecules interact with immune receptors such as Dectin-1 and can shift the immune environment towards tolerance and suppression rather than active tumour-fighting. Tumour microenvironment changes – According to a 2026 review in Gut Microbes, fungi and their metabolites remodel the tumour microenvironment through metabolic reprogramming, including depletion of critical amino acids and production of immunosuppressive short-chain fatty acids. Microbial balance disruption – When bacterial diversity drops following antibiotic use, poor diet, or illness, fungi overgrow and disrupt the anti-tumour immune activity that bacteria normally support. This balance is now considered a critical regulator of cancer treatment response. Impaired CD8 T cell activity – The Cedars-Sinai study found that fungal overgrowth impairs the activity of cytotoxic CD8 T cells (the immune cells most critical for killing cancer cells) while increasing immunosuppressive macrophages in the tumour microenvironment. A Fast-Moving Field: Research Milestones The relationship between the gut microbiome and immunotherapy is one of oncology’s fastest-growing research areas. Research published in iMeta (2024) documents the following milestones: A landmark review in Nature Reviews Drug Discovery (2025) concludes that the gut microbiome is now recognised as a key modulator of immunotherapy efficacy, with clinical trials of microbiome-based interventions actively underway. The Future of Microbiome-Driven Cancer Care Researchers highlighted in a Nature collection on the microbiome in cancer (2024) note that tumours contain both bacteria and fungi, and that their presence is proving useful in detecting cancers, categorising them, and predicting whether specific interventions will work. Potential future strategies include: A 2026 review in Gut Microbes concludes that fungi and their metabolites may enhance tumour immunogenicity and reduce therapeutic resistance, with antifungal-based therapies showing particular promise as an adjunct to immunotherapy. What This Means for Cancer Patients Cancer therapy is no longer just about targeting tumour cells. The microbial ecosystem inside the body plays a significant role in determining treatment success. As Dr. David Underhill of Cedars-Sinai stated after the landmark study: “It would be really handy to be able to characterise a patient’s microbiome, both bacterial and fungal, and determine their expected prognosis, or how they will respond to radiation therapy, chemotherapy, or immunotherapy. Then we would like to see whether it is feasible to change that microbiome to make those therapies work better.” The gut microbiome, including its fungal residents, may soon become one of oncology’s most important biomarkers and therapeutic targets. FAQs Can gut fungi actually affect cancer treatment outcomes? Yes. Research in Cancer Cell shows that gut fungi directly suppress anti-tumour immune responses after radiation therapy. Antifungal treatment restored immune activity and improved outcomes in preclinical models of breast cancer and melanoma. Why do some patients not respond to immunotherapy? Multiple factors contribute, including tumour genetics, immune profile, and gut microbiome composition. Only 20 to 40% of patients in certain groups respond to immunotherapy. Scientists believe optimising the mycobiome may help improve these rates. What is Dectin-1, and why does it matter in cancer? Dectin-1 is an immune receptor that senses fungi. Higher Dectin-1 expression in
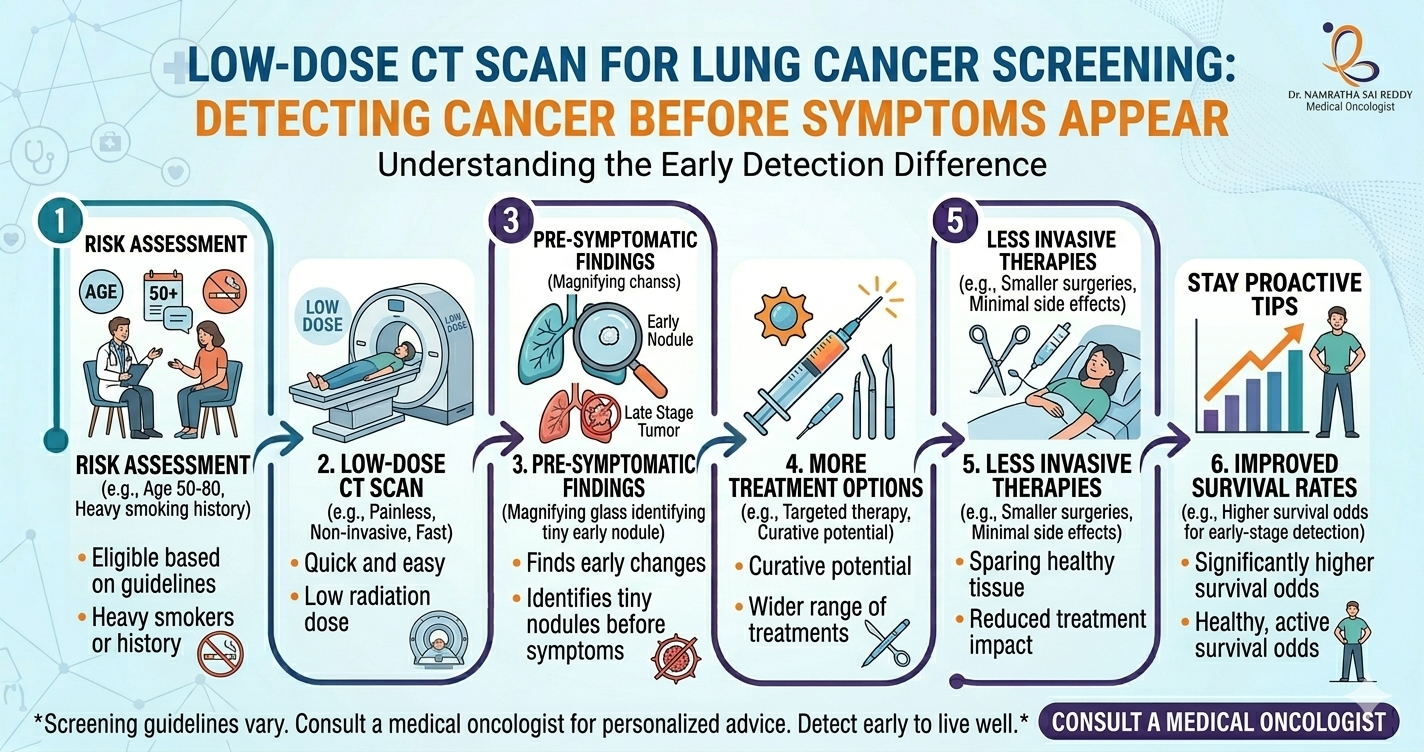
Low-Dose CT Scan for Lung Cancer Screening: Detecting Cancer Before Symptoms Appear
Lung cancer remains one of the most serious global health challenges. One major reason is that the disease often develops without noticeable symptoms in its early stages, leading to delayed diagnosis and limited treatment options. Advances in medical imaging have changed this reality. One of the most important breakthroughs in cancer screening is the Low-Dose CT (LDCT) scan, which allows doctors to detect lung cancer much earlier than traditional methods. Research has shown that screening high-risk individuals with LDCT can reduce lung-cancer deaths by about 20% compared with chest X-rays, demonstrating the powerful role of early detection in saving lives. Key Takeaways What Is a Low-Dose CT Scan for Lung Cancer Screening? A low-dose CT scan is a specialised imaging test designed to detect lung cancer in people who are at higher risk of developing the disease. Unlike a standard CT scan, LDCT uses significantly less radiation while still producing detailed images of the lungs. This enables doctors to detect very small nodules or abnormalities that may indicate early cancer, often before symptoms appear. How the technology works Low-dose CT scans use advanced imaging technology to capture multiple cross-sectional images of the lungs from different angles. A computer then processes these images to create a detailed view of lung tissue. This level of precision allows doctors to detect nodules as small as a few millimetres in size, which would typically not be visible on a standard chest X-ray. Key features of LDCT screening Because lung cancer often progresses silently, this technology has become one of the most valuable tools in early cancer detection. Why Is Early Detection of Lung Cancer So Important? Early detection dramatically improves survival rates. Lung cancer often does not cause noticeable symptoms until the disease has progressed. When symptoms such as persistent cough, chest pain, fatigue, or weight loss appear, the cancer may already have spread. Detecting lung cancer earlier can significantly improve treatment outcomes. Statistics highlighting the importance of early detection Benefits of detecting cancer early Early diagnosis may allow doctors to: For many patients, early detection can mean the difference between curative treatment and complex long-term management. Who Should Consider Low-Dose CT Screening? Adults at high risk, especially long-term smokers. Not everyone requires lung cancer screening. The benefits of LDCT screening are greatest in individuals with higher risk factors, particularly long-term smokers. Recommended screening group Medical guidelines generally recommend screening for individuals who: Understanding pack-years A pack-year is a measurement used to estimate long-term smoking exposure. Examples include: Both scenarios equal 20 pack-years of smoking exposure. Other potential risk factors Some individuals may also have an elevated risk due to: A healthcare provider can help determine whether screening is appropriate based on individual risk factors. What Happens During a Low-Dose CT Scan? A fast, painless imaging test of the lungs. Many patients feel anxious before undergoing imaging tests. However, the low-dose CT scan is simple, quick, and painless. Step-by-step overview The entire process usually takes less than 10 minutes, and no recovery time is needed. Important features of the procedure Because of its simplicity and low radiation exposure, LDCT is considered safe for annual screening in eligible individuals. What Can a Low-Dose CT Scan Detect? Tiny nodules and early signs of lung cancer. One of the biggest advantages of LDCT scans is their ability to detect very small lung abnormalities that may not appear on standard imaging tests. Possible findings on the scan It is important to understand that most lung nodules detected during screening are not cancerous. What happens if a nodule is detected? If an abnormality appears on the scan, doctors may recommend: Careful monitoring helps determine whether a nodule is harmless or requires further evaluation. What Are the Benefits of Low-Dose CT Screening? Low-dose CT screening offers several important advantages, especially for individuals at higher risk. Major benefits include Early cancer detection The scan can detect tumours before symptoms develop, improving treatment success. Improved survival rates Early-stage lung cancer is often more treatable and may be cured through surgery. Non-invasive procedure The screening test is quick, painless, and does not require hospitalisation. Better monitoring of lung health The scan may also detect other lung conditions that require medical attention. Are There Any Risks or Limitations? While LDCT screening provides many benefits, it is important to understand potential limitations. False positives Sometimes scans may detect nodules that appear suspicious but are not cancerous. This may require additional testing. Radiation exposure Although the radiation dose in LDCT scans is significantly lower than that of standard CT scans, repeated imaging over time may increase cumulative exposure. Overdiagnosis In rare cases, screening may detect very slow-growing cancers that might not have caused symptoms during a person’s lifetime. Because of these factors, screening is recommended primarily for individuals who meet established risk criteria. How Can People Reduce Their Risk of Lung Cancer? While screening helps detect cancer early, prevention remains the most effective strategy. Avoid smoking and maintain healthy habits. Steps that reduce lung cancer risk Combining preventive measures with appropriate screening provides the best protection against lung cancer. Prioritize Prevention and Early Detection for Better Lung Health Low-dose CT scans represent a major advancement in the early detection of lung cancer. By identifying abnormalities before symptoms appear, this screening method allows doctors to intervene earlier and improve treatment outcomes. For individuals with a significant smoking history or other risk factors, discussing low-dose CT screening with a healthcare professional may be an important step toward protecting long-term health. Early detection not only improves survival rates but also offers patients a better chance at effective treatment and recovery. Frequently Asked Questions (FAQs) 1. What is a low-dose CT scan? A low-dose CT scan is an imaging test that uses minimal radiation to detect early lung abnormalities that may indicate cancer. 2. Who should undergo lung cancer screening? Adults aged 50–80 with a significant smoking history or those who quit smoking within the past 15 years are typically recommended for screening. 3. Is the low-dose CT scan
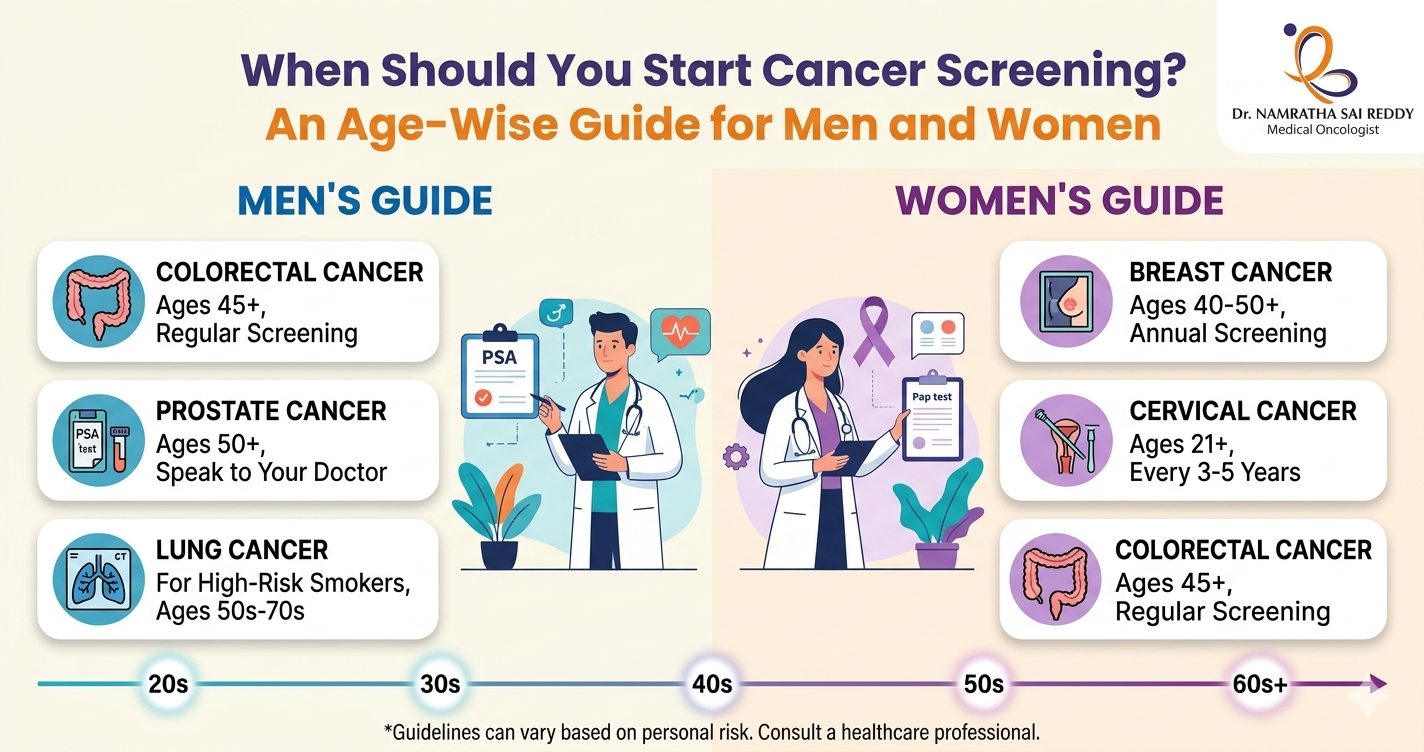
When Should You Start Cancer Screening? An Age-Wise Guide for Men and Women
• Most cancer screenings begin between the ages of 21 and 50. Missing or delaying them is one of the biggest reasons cancers go undetected until they’re harder to treat. • Women start cervical screening at 21, mammograms at 40; everyone starts colorectal screening at 45; men discuss prostate screening at 50. Knowing your age-based schedule removes the guesswork. • Pap smears and colonoscopies can catch and remove precancerous cells before they turn malignant, making them true prevention tools. • Family history, genetic mutations (BRCA, Lynch syndrome), smoking, or prior precancerous conditions can move your screening start date earlier. Talk to your doctor if any of these apply. • Regular screening, even when you feel completely fine, is what makes early detection possible. Cancer screening should begin at age 21 for women (cervical cancer) and age 45 for both men and women (colorectal cancer). Women should start mammograms at 40, and men should discuss prostate screening at 50. The right age depends on cancer type, gender, and personal risk factors. Cancer often develops silently, without obvious symptoms in its early stages. That is why screening plays a crucial role in preventive healthcare. Cancer screening tests help detect abnormal cells or early-stage cancers before symptoms appear, allowing treatment to begin when it is most effective. Why Cancer Screening Is Important Cancer screening helps detect disease before symptoms appear. Early detection significantly improves treatment outcomes and survival rates. Most early-stage cancers have survival rates of 80 to 90 percent, while advanced-stage cancers are far more difficult to treat. According to the AACR Cancer Progress Report 2024, overall cancer death rates in the United States fell by 33 percent between 1991 and 2021, translating to an estimated 4.1 million lives saved, a trend driven in large part by earlier detection through screening. Screening also identifies precancerous changes, allowing doctors to treat them before cancer develops. For example, colonoscopies and Pap tests can prevent certain cancers entirely, not just detect them early. Key benefits of cancer screening include: • Early diagnosis and timely treatment • Improved survival rates • Less aggressive treatment options • Better quality of life • Prevention of certain cancers Ages 21 to 29: Early Preventive Screening In this age group, routine screening begins primarily for women. For Women Cervical Cancer Screening Women should begin Pap smear screening at age 21, regardless of sexual activity. The recommended schedule is a Pap test every three years between the ages of 21 and 29. Pap tests detect abnormal cervical cells that may eventually develop into cervical cancer. Breast Awareness Women should begin monthly breast self-examinations from age 20 and consult a doctor if they notice lumps, breast pain, or changes in breast shape or skin. For Men Routine cancer screening is not typically recommended for most men in this age group unless there are specific risk factors. Men should still attend regular health check-ups that include general examinations for skin changes, lumps or swelling, and abnormal growths. Men with a strong family history of cancer may require earlier screening discussions with their doctor. Ages 30 to 39: Expanding Screening In your thirties, screening continues for cervical cancer and preventive health evaluations. For Women Cervical Cancer Women aged 30 to 65 should undergo either a Pap smear plus HPV test every five years, or a Pap smear alone every three years. HPV testing helps detect high-risk strains of human papillomavirus, which are responsible for approximately 99 percent of all cervical cancers. Breast Cancer Routine mammograms are not yet recommended for average-risk women in their thirties. Those with a family history, BRCA gene mutation, or other elevated risk factors should discuss earlier screening with their doctor. For Men Routine screening is still limited at this age. Men should monitor their health and consult a doctor if they notice persistent fatigue, unexplained weight loss, or lumps and unusual swelling. Men with genetic or family cancer risk may require earlier screening discussions. Ages 40 to 49: An Important Screening Stage Cancer screening becomes more structured during this decade. For Women Breast Cancer Women should begin annual mammograms starting at age 40. Mammography can detect breast cancer before symptoms appear, significantly improving survival rates. Thanks in part to early mammography, most breast cancers today are diagnosed at stage I, which carries a five-year survival rate of close to 100 percent. Cervical Cancer Continue screening with a Pap plus HPV test every five years, or a Pap test alone every three years. For Men (High Risk) Prostate Cancer Men with increased risk, such as a family history of prostate cancer or of African American descent, should discuss screening with their doctor starting at age 45. Screening may include a PSA (prostate-specific antigen) blood test and a digital rectal examination (DRE). For Both Men and Women Colorectal Cancer Routine screening for colorectal cancer should begin at age 45 for most adults. Thanks to screening, colorectal cancer death rates have fallen by 47 percent in men and 44 percent in women over recent decades. Ages 50 to 64: Comprehensive Cancer Screening In your fifties and early sixties, screening becomes essential across multiple cancer types. For Women Women should continue annual mammograms. Cervical cancer screening continues with a Pap plus HPV test every five years, or a Pap smear every three years. For Men Prostate Cancer Men aged 50 and above should discuss prostate cancer screening with their doctor. Testing may include a PSA blood test and a digital rectal exam. Shared decision-making, weighing the potential benefits and harms of screening is recommended. For Both Men and Women Colorectal Cancer Recommended screening methods include a colonoscopy every ten years, annual stool tests (FIT or FOBT), flexible sigmoidoscopy every five years, or a stool DNA test every three years. Colonoscopy remains the gold standard because it can both detect and remove precancerous polyps during the same procedure. Lung Cancer Adults aged 50 to 80 with a heavy smoking history like 20 pack-years
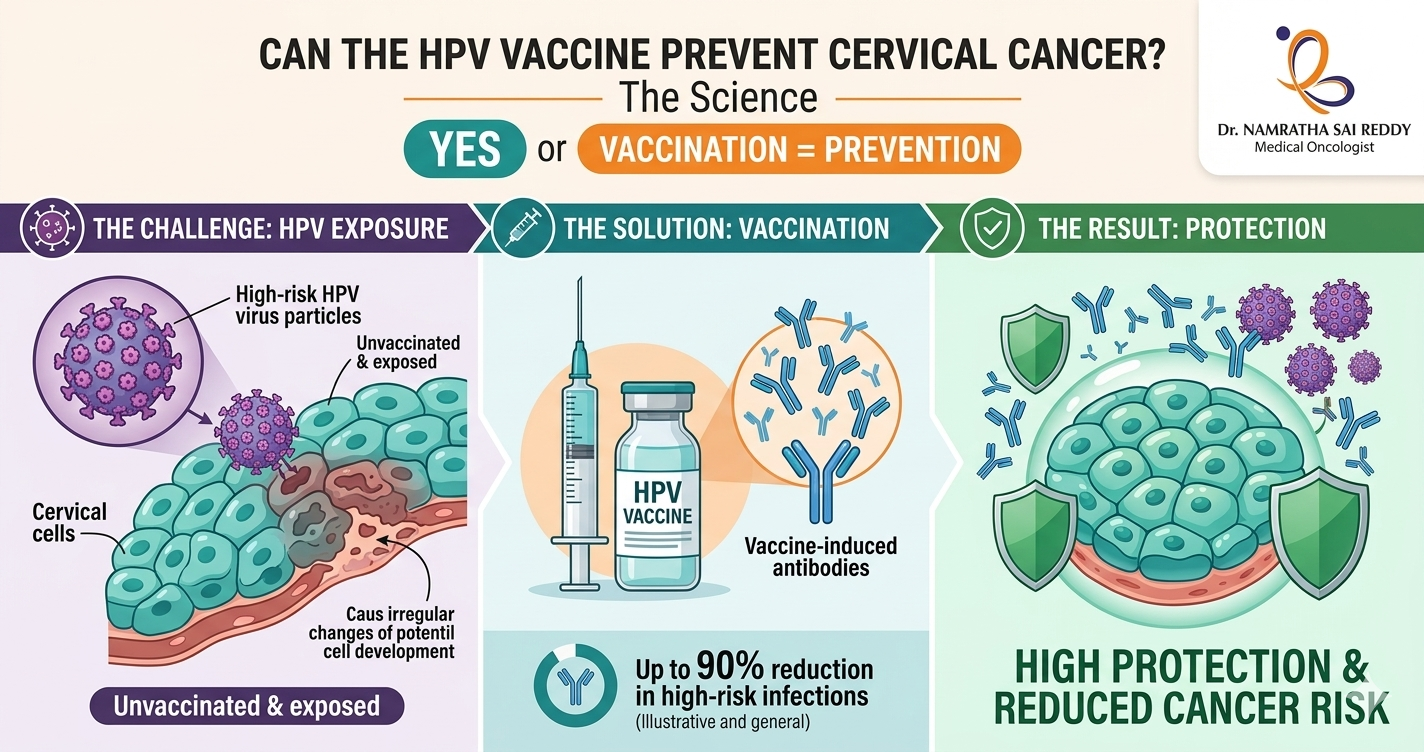
Can the HPV Vaccine Prevent Cervical Cancer? Here’s the Science
Yes, and the evidence is overwhelming. HPV vaccination reduces cervical cancer risk by up to 88–90% when given before age 17. In India, where a woman dies of cervical cancer every seven minutes, the HPV vaccine is not just a health tool; it is a national emergency intervention. India launched its nationwide free vaccination programme on 28 February 2025, targeting 11.5 million girls aged 14. Key Takeaways • India carries the world’s highest cervical cancer death toll. Over 79,906 women died from cervical cancer in India in 2022, more than 22% of all global deaths and a new case is diagnosed every four minutes. • HPV causes virtually all cervical cancers in India. HPV types 16 and 18 alone account for 76.7% of cervical cancer cases in India, making targeted vaccination extraordinarily effective. • Early vaccination delivers the strongest protection. Girls vaccinated before age 14 need only 2 doses and gain up to 90% risk reduction. Waiting until adulthood significantly reduces the vaccine’s benefit. • India now has an affordable home-grown vaccine. CERVAVAC by the Serum Institute of India costs ₹1,400–2,500 per dose in private clinics — and is free at government centres for eligible girls under the national programme. • Vaccination and screening must go together. The HPV vaccine does not protect against all high-risk strains. Regular Pap smears or HPV DNA tests remain essential, yet India’s current cervical cancer screening rate is just 2%. The Link Between HPV and Cervical Cancer Human Papillomavirus (HPV) is the most common sexually transmitted infection worldwide. While most HPV infections clear on their own, certain high-risk strains can persist and cause cancers of the cervix, vagina, vulva, penis, anus, and throat. Cervical cancer is the most common HPV-related cancer in women. According to the WHO’s Global Strategy for Cervical Cancer Elimination (2025), approximately 660,000 new cases and 350,000 deaths occurred in 2022 alone, with the highest burden in low- and middle-income countries. In India, cervical cancer claims one woman’s life every eight minutes and accounts for approximately 1.23 lakh new cases per year. Approximately 99.7% of all cervical cancers are caused by untreated or chronic HPV infection, making it one of the most preventable of all cancers. HPV types 16 and 18 alone are responsible for around 70% of all cervical cancer cases globally. How the HPV Vaccine Prevents Cervical Cancer The HPV vaccine is a preventive injection, not a treatment. It works by training your immune system to recognise specific high-risk HPV strains before exposure. When a vaccinated person later encounters the virus, their immune system neutralises it before it can establish a persistent infection that leads to cancer. Think of it as the only shot specifically designed to prevent cancer. The HPV vaccine is not just a vaccine against a virus; it is a vaccine against cancer. The “shot to prevent cervical cancer” and the “injection to prevent cervical cancer” both refer to the HPV vaccine, available in India as Gardasil, Gardasil 9, Cervarix, and CERVAVAC. It is administered as an intramuscular injection into the upper arm. HPV Vaccine Types Available in India As of 2025, India has four approved HPV vaccines. Each differs in the number of HPV strains covered, the approved age range, and cost. Gardasil 9 (Nonavalent) • Strains covered: HPV 6, 11, 16, 18, 31, 33, 45, 52, 58 (9 strains) • Age range: 9–45 years • Broadest available protection against HPV-related cancers and genital warts Gardasil 4 (Quadrivalent) • Strains covered: HPV 6, 11, 16, 18 • Age range: 9–26 years • Also prevents genital warts Cervarix (Bivalent) • Strains covered: HPV 16, 18 • Age range: 9–25 years • Targets the two main cancer-causing HPV strains CERVAVAC (Made in India – Bivalent) • Strains covered: HPV 16, 18 • Age range: 9–26 years • Developed by the Serum Institute of India, the most affordable option available • Launched in 2023 as India’s first indigenously developed HPV vaccine HPV Vaccine Dosing Schedule: 2-Dose vs 3-Dose The number of doses you need depends on your age when you receive your first shot. The younger you are when you are vaccinated, the stronger your immune response and the fewer doses you will need. 2-Dose Schedule (Ages 9–14) Children in this age group require only two doses because their immune response is stronger. 3-Dose Schedule (Ages 15 and Older) The CDC recommends routine vaccination at ages 11 or 12 (beginning as early as age 9), well before potential exposure to HPV. Immunocompromised individuals aged 9–26 require three doses regardless of their age at first vaccination. Note on single-dose schedules: As of early 2026, 89 countries, including the United States, have adopted a single-dose schedule for national immunisation programmes, particularly for Gavi-eligible low-income countries. Multi-dose schedules remain standard in India’s private market. Why Is the HPV Vaccine Not Recommended After Age 26? This is one of the most common questions about the HPV vaccine. The answer lies in biology and health economics. The CDC’s Advisory Committee on Immunisation Practices (ACIP) does not recommend routine HPV vaccination for adults over 26 for the following reasons: 1. Prior Exposure Reduces Benefit Most sexually active adults have already been exposed to one or more HPV strains by their mid-20s. Since the vaccine prevents infection but cannot treat existing HPV, its protective benefit is significantly lower in this age group. 2. Limited Cost-Effectiveness at the Population Level A landmark study by Harvard T.H. Chan School of Public Health, published in PLOS Medicine, found that vaccinating adults beyond age 26 provides limited health benefit at the population level at a substantial cost. The study modelled HPV-associated cancer and genital wart outcomes across multiple age-group scenarios. 3. FDA Approval Up